












-
Colorectal cancer (CRC) is the third most common cancer in the US (~150,000 cases/year); about 70% of patients with stage II–III disease live ≥ 5 years beyond diagnosis[1] and are susceptible to late treatment effects[2,3]. Standard-of-care multi-drug chemotherapy treatment regimens (e.g., folinic acid, fluorouracil, and oxaliplatin [FOLFOX]; capecitabine and oxaliplatin [CAPOX]) for CRC include oxaliplatin[4], a neurotoxic drug that damages both the central and peripheral nervous systems[5]. Chemotherapy-induced peripheral neurotoxicity (CIPN) is a common manifestation of oxaliplatin-induced neurotoxicity.
Chemotherapy-induced neurotoxicity poses a major health risk for cancer survivors. CIPN is experienced by nearly all patients (94%) who receive oxaliplatin, but in varying degrees of severity and chronicity[4,6]. CIPN is characterized by upper and lower extremity numbness, tingling, and pain. Further, CIPN poses a major health risk because it causes impaired function and falls[7−10], socioeconomic disadvantage (e.g., negative impact on work)[11−13], and poor quality of life (QOL)[14−17].
Although oxaliplatin-associated patient-reported neurotoxicity symptoms have been extensively described, we do not yet understand which patients are at the highest risk for severe adverse outcomes and should be considered for early interventions such as the selection of less neurotoxic chemotherapy treatments, earlier dosage reductions, or other preventive interventions as they become available. Lastly, while we know that CIPN is pervasive and disabling, no effective preventive interventions for high-risk patients exist[18−22].
Despite numerous attempts to test promising interventions, the research community has failed to find efficacious interventions, and this failure is partially due to the paucity of standardized, feasible, reliable, valid, and sensitive measures that can detect clinically important changes in CIPN resulting from an effective intervention. It is time to invest research dollars to explore new objective CIPN measurement methods that will minimize response bias and are feasible for use in large, multisite clinical trials. More specifically, we propose that a serum biomarker could be used in conjunction with subjective patient-reported outcome measures (PROMs) to quantify intervention efficacy. While extensively validated, easy to administer, and important for understanding the patient's perceptions and experiences, PROMs have limitations when used as the sole outcome measure in a clinical trial. More specifically, subjective PROMs can facilitate a high placebo response, which in turn can compromise statistical power and the ability to show that a promising intervention is better than the placebo[23]. A recent example illustrates this point; a completed multisite, randomized, double-blind, placebo-controlled Phase II trial that was conducted within the National Cancer Institute's National Clinical Trials Network (Clinicaltrials.gov Identifier: NCT04137107) failed to show that duloxetine was more effective than placebo to prevent oxaliplatin-induced neurotoxicity[24], possibly, in part, due to a high placebo response rate. The primary outcome was measured using a validated PROM. While approximately 66% of duloxetine-treated patients did not develop oxaliplatin-induced neurotoxicity, a high placebo response rate (68%) may have confounded the findings. Placebo response is well-recognized as a confounder in failed intervention trials testing drugs for pain and psychiatric indications, ranging from 25% to 50%, and appears to be increasing over time[25−27]. The inclusion of an objective biomarker as an additional CIPN outcome measure in the duloxetine trial may have allowed the investigators to evaluate duloxetine efficacy more objectively, eliminating response bias due to placebo response.
Prior to the more recent reliance on PROMs to assess primary outcomes in CIPN clinical trials, clinical grading scales (e.g., Common Terminology Criteria for Adverse Events [CTCAE]) were the mainstay outcome measures. Although it is easy to use clinician grading scales to identify Grade 2 or 3 neurotoxicity as a point when something should be done to mitigate severe CIPN, these insensitive and unreliable grading scales underestimate CIPN severity. However, cumbersome objective neurologic assessments (e.g., nerve conduction, neurologic exams, skin biopsy, functional assessments) are not necessarily better because they are infeasible for routine use in busy practice settings or multi-site intervention studies[28].
Instead, what if we could test intervention efficacy using a more sensitive and clinically feasible test, like a simple serum biomarker test obtainable from a routine blood draw? Serum neurofilament light chain (sNfL) shows promise as an outcome measure in intervention studies based on published research suggesting mechanistic connections with chemotherapy-induced neurotoxicity. sNfL is a protein found in large, myelinated nerve axons[29,30]. Elevated levels indicate axonal nerve damage in patients with cognitive neurodegenerative conditions such as Alzheimer's disease[31,32] and dementia[33]. Studies also demonstrate that sNfL levels increase following neurotoxic chemotherapy treatment with vincristine in animals[34], and paclitaxel[35,36] and oxaliplatin[37] administration in patients with breast and colorectal cancer, respectively. Three studies suggest that sNfL levels steadily increase as cumulative neurotoxic chemotherapy dosage increases, and levels obtained early in the patient's treatment course can predict the development of chronic CIPN at chemotherapy completion[35,37,38]. One study showed that an increase of 36 pg/mL from baseline was associated with a > 50% probability of developing CIPN[36]. Informed by this published evidence, the objective of this pilot study was to validate a promising CIPN biomarker, serum neurofilament light chain (sNfL), for use as an objective outcome measure in future oxaliplatin-induced CIPN prevention trials.
-
The study objective was addressed using a prospective, longitudinal, descriptive design. Eligible patients had stage II–III colorectal cancer, were ≥ 18 years of age, had a Karnofsky performance status score ≥ 70, and were scheduled to receive oxaliplatin-containing adjuvant treatment regimens. Other eligibility criteria were: (1) no prior neurotoxic chemotherapy treatment; (2) no preexisting clinical or preclinical peripheral neurotoxicity (e.g., diminished deep tendon reflexes) from any cause; (3) neurologic or psychiatric conditions (e.g., schizophrenia, bipolar disorder, major depressive episode, total brain irradiation, history of stroke, dementia diagnosis, brain tumor, spinal, or brain metastases) that would interfere or complicate the assessments; (4) no chronic use of concomitant antiepileptic drugs, antidepressants, and major analgesics (e.g., gabapentin, pregabalin, venlafaxine), unless stable dosing had been maintained for 3 months prior to enrollment; and (5) no concomitant use of nonpharmacologic CIPN interventions (known or hypothesized) (e.g., cryotherapy, compression therapy, acupuncture).
Convenience sampling methods were used to recruit study participants at the University of Alabama at Birmingham's (UAB) O'Neal Comprehensive Cancer Center. Single-center enrollment occurred between November 4, 2021, and May 20, 2025. The study was approved by UAB's Institutional Review Board (IRB-300007934-021), and all participants provided signed informed consent.
Study staff screened potentially eligible patients through medical record review and discussion with treating physicians, nurses, and patient navigators. Data were collected by two trained research nurses during regularly scheduled clinical visits or at an alternative mutually convenient time. The research nurses underwent didactic and hands-on training regarding the administration of surveys and peripheral neurotoxicity physical examination methods (e.g., deep tendon reflexes, pin prick and vibratory sensation, and strength assessments), which were scored using the validated Total Neuropathy Score-Nurse © (TNSn©)[39,40]. Nurse assessors generally followed the same patients over time to minimize threats to data reliability that can occur if there is more than one rater, and to facilitate detection of each patient's change over time.
Data were collected at four timepoints: (1) prior to receiving the first oxaliplatin treatment (B-baseline); (2) in the middle of oxaliplatin treatment; (3) at the end of oxaliplatin treatment (EOT), and 3 months after the last oxaliplatin treatment. To minimize attrition, participants received a US
${\$} $ The study was powered to detect a moderate correlation (Spearman ρ = 0.5) at a significance level of 0.05 with 80% statistical power, based on a sample of 28 patients. All participants completed a baseline demographic survey to collect data about sex and race. Oxaliplatin cumulative dose data were abstracted from the medical record. Peripheral neurotoxicity was assessed at each time point using both objective and subjective measures. We quantified CIPN using the TNSn©[41], a validated reduced version of the original TNS©. The TNSn© is a reduced version of the Total Neuropathy Score that can be used by a non-neurologist clinician (e.g., nurse, other healthcare professional) and retains key subjective and quick objective elements (sensory symptoms, pin-prick, and vibration testing) while improving feasibility for repeated assessments in oncology clinics. Prior multicenter and validation studies show that TNS© variants have superior sensitivity to detect mild-to-moderate CIPN compared with clinician-grade scales such as the CTCAE, and the TNSn© preserves acceptable reliability and convergent validity in chemotherapy populations[41]. The reduced TNSn© (Supplementary Table S1a) captures subjective and objective neurological physical examination assessments: subjective numbness, tingling and pain in the arms and legs, motor and autonomic symptoms, and bilateral pin prick and vibratory sensibility. Each item was scored from 0 to 4 and summed to create a composite score ranging from 0–20, with higher scores equating to more severe neurotoxicity.
Peripheral neurotoxicity was also assessed using a validated subjective PROM, the CIPN6. The CIPN6 is a six-item survey that contains items from the EORTC Chemotherapy-Induced Peripheral Neuropathy (CIPN) 20-item questionnaire (Supplementary Table S1b)[42]. Because oxaliplatin causes mainly sensory neurotoxicity, inclusion of all CIPN20 items that assess motor or autonomic neurotoxicity would compromise sensitivity, thereby justifying our selection of only six sensory items[38]. The six-item subset assesses sensory CIPN (numbness, tingling, burning/shooting pain) in the upper and lower extremities; items are scored from 1 (not at all) to 4 (very much). The total score range is from 6 to 24, with higher scores reflecting worse CIPN. Published literature provides strong evidence that a six-item subset (CIPN-6) is reliable, sensitive, valid, and responsive[43].
To quantify sNfL levels, we collected 5 mL of whole blood in serum separator tubes at each time point. Samples were labelled with a sticker indicating: (1) patient code/ID number; (2) date and time of blood collection; and (3) recruitment site—(UAB O'Neal Comprehensive Cancer Center). The samples were centrifuged at 2,000 g for 10 min at room temperature to obtain the serum from the clotted blood. Serum samples were stored at −20°C as aliquots of 0.5–2 milliliters until a sufficient batch had accumulated and could be measured using UmanDiagnostics NF-Light ELISA (Cat#: 20-8002)[44].
Descriptive statistics (frequency, mean, median, range, standard deviation [SD]) were used to describe demographics, peripheral neurotoxicity scores, and sNfL levels for the study sample. Longitudinal trends in TNSn©, CIPN6, and sNfL were graphed over the 3-month assessment period. Changes in mean scores from baseline to the EOT and 3-month timepoints were assessed using the general linear mixed model (LMM) with random intercept and first-order autoregressive (AR[1]) variance structure, controlling for age, sex, race, and cumulative chemotherapy dose. The adjusted changes were reported as mean and 95% confidence interval (CI), and p values with Bonferroni correction. The missing data were handled by the full-information maximum likelihood method. Spearman correlation coefficients were calculated to assess correlations between sNfL and the two validated measures of CIPN (TNSn© and CIPN6) at each time point. The general linear mixed model was also applied to evaluate the longitudinal association of sNfL with TNSn© and CIPN6, controlling for age, sex, race, and cumulative chemotherapy dose.
-
Twenty-eight patients participated in the study. The mean participant age was 54.8 years (range 38–79 years, SD 11.6). Most participants were male (n = 19, 67.9%) and Caucasian (n = 22, 78.6%) (Table 1).
Table 1. Baseline characteristics (N = 28).
Variable N (%) or Mean (SD) Age Mean (SD) 54.8 (11.6) Median (range) 54.5 (38.0–79.0) Sex Male 19 (67.9%) Female 9 (32.1%) Race Caucasian 22 (78.6%) African American 5 (17.9%) Other 1 (3.6%) Cumulative chemotherapy dose (mg) Mean (SD) 624.0 (181.7) Median (range) 648.5 (259.9–1,019.6) Patients received an average of 6.7 (SD 2.8; median 6) oxaliplatin treatments (range 2–12) over 13 weeks (once every 2 weeks). The mean oxaliplatin cumulative dose received by EOT was 624.0 mg (SD = 181.7; range = 259.9–1,019.6). Table 2 shows the mean, median, minimum, maximum, and SD for sNfL, CIPN6, and TNSn© at each time point. Baseline sNfL values (n = 28) ranged from 1.7 to 49.4 pg/mL (mean 23.8 ± 14.1). We did not apply a pre-specified abnormal cut-off in the protocol because there is no universally accepted threshold for oxaliplatin CIPN.
Table 2. Descriptive statistics of outcomes by time.
Variable Mean SD Median Minimum Maximum sNfL (pg/mL) Baseline (n = 28) 23.8 14.1 19.6 1.7 49.4 Mid-treatment (n = 24) 27.6 16.0 21.0 8.6 72.3 End of treatment (n = 23) 46.7 39.8 44.6 2.0 160.0 3 months post (n = 20) 61.1 47.6 51.1 2.0 160.0 CIPN6 Baseline (n = 28) 6.6 1.5 6.0 6.0 12.0 Mid-treatment (n = 21) 9.5 4.0 9.0 6.0 20.0 End of treatment (n = 25) 11.7 5.0 10.0 6.0 23.0 3 months post (n = 19) 12.4 5.6 13.0 6.0 24.0 TNSn© Baseline (n = 28) 0.5 0.9 0.0 0.0 4.0 Mid-treatment (n = 23) 1.0 1.3 0.0 0.0 4.0 End of treatment (n = 24) 2.6 2.7 2.0 0.0 9.0 3 months post (n = 18) 2.9 3.1 2.5 0.0 10.0 All scores increased from baseline to the 3-month time period. Table 3 illustrates that there were statistically significant changes over time across all three CIPN measures (TNSn©, CIPN6, sNfL).
Table 3. Change from baseline.
Outcomes Mean ± SD Adjusted change from
baseline* Mean [95% CI]p-value** sNfL(pg/mL) Baseline (n = 28) 23.8 ± 14.0 Mid-treatment (n = 24) 27.6 ± 16.0 3.4 [−11.5, 18.4] 0.6501 End of treatment (n = 23) 46.7 ± 39.8 21.8 [6.6, 37.0] 0.0168 3 months post (n = 20) 61.1 ± 47.6 36.9 [21.1, 52.8] < 0.0001 CIPN6 Baseline (n = 28) 6.6 ± 1.5 Mid-treatment (n = 21) 9.5 ± 4.0 2.6 [0.5, 4.6] 0.0525 End of treatment (n = 25) 11.7 ± 5.0 5.1 [3.2, 7.1] < 0.0001 3 months post (n = 19) 12.4 ± 5.6 6.4 [4.2, 8.6] 0.0001 TNSn© Baseline (n = 28) 0.5 ± 0.9 Mid-treatment (n = 23) 1.0 ± 1.3 0.5 [−0.5, 1.5] 0.8610 End of treatment (n = 24) 2.6 ± 2.7 2.2 [1.2, 3.2] < 0.0001 3 months post (n = 18) 2.9 ± 3.1 2.6 [1.5, 3.7] < 0.0001 * Adjusted for age, sex, race, and cumulative chemotherapy dose with LMM.
** Bonferroni corrected.Figures 1, 2, and 3 graphically illustrate the consistent rise in CIPN assessment measure values, demonstrating worsening neurotoxicity over time and a coasting phenomenon because neurotoxicity continued to worsen for 3 months after stopping oxaliplatin treatment.
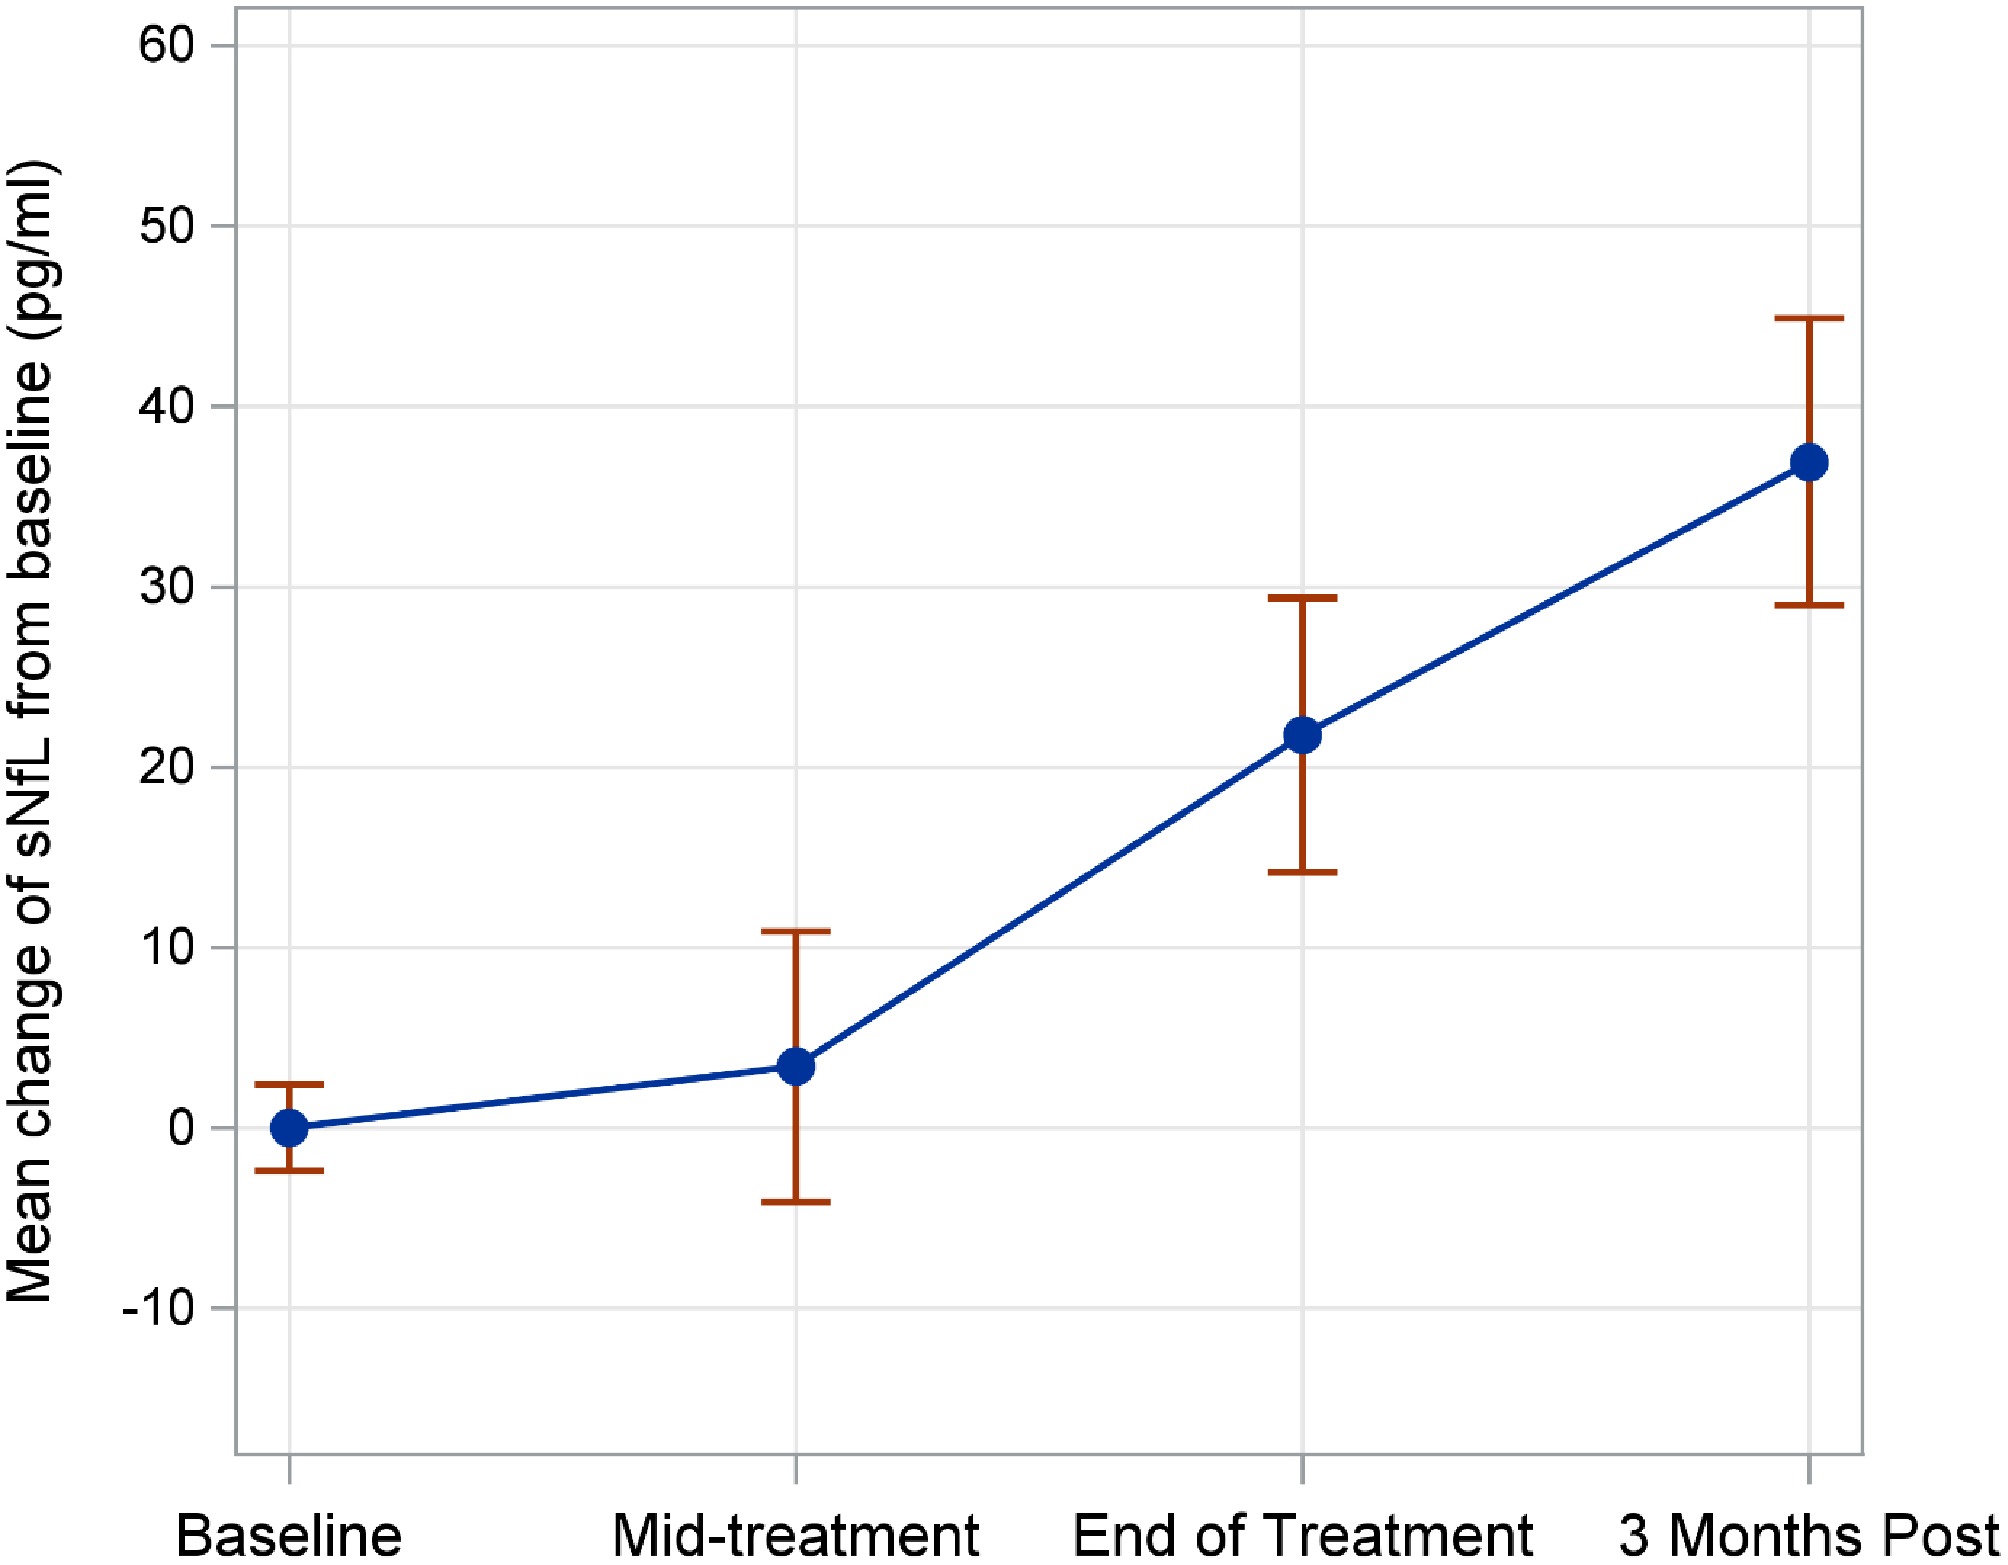
Figure 1.
Mean change of sNfL from baseline (pg/mL).
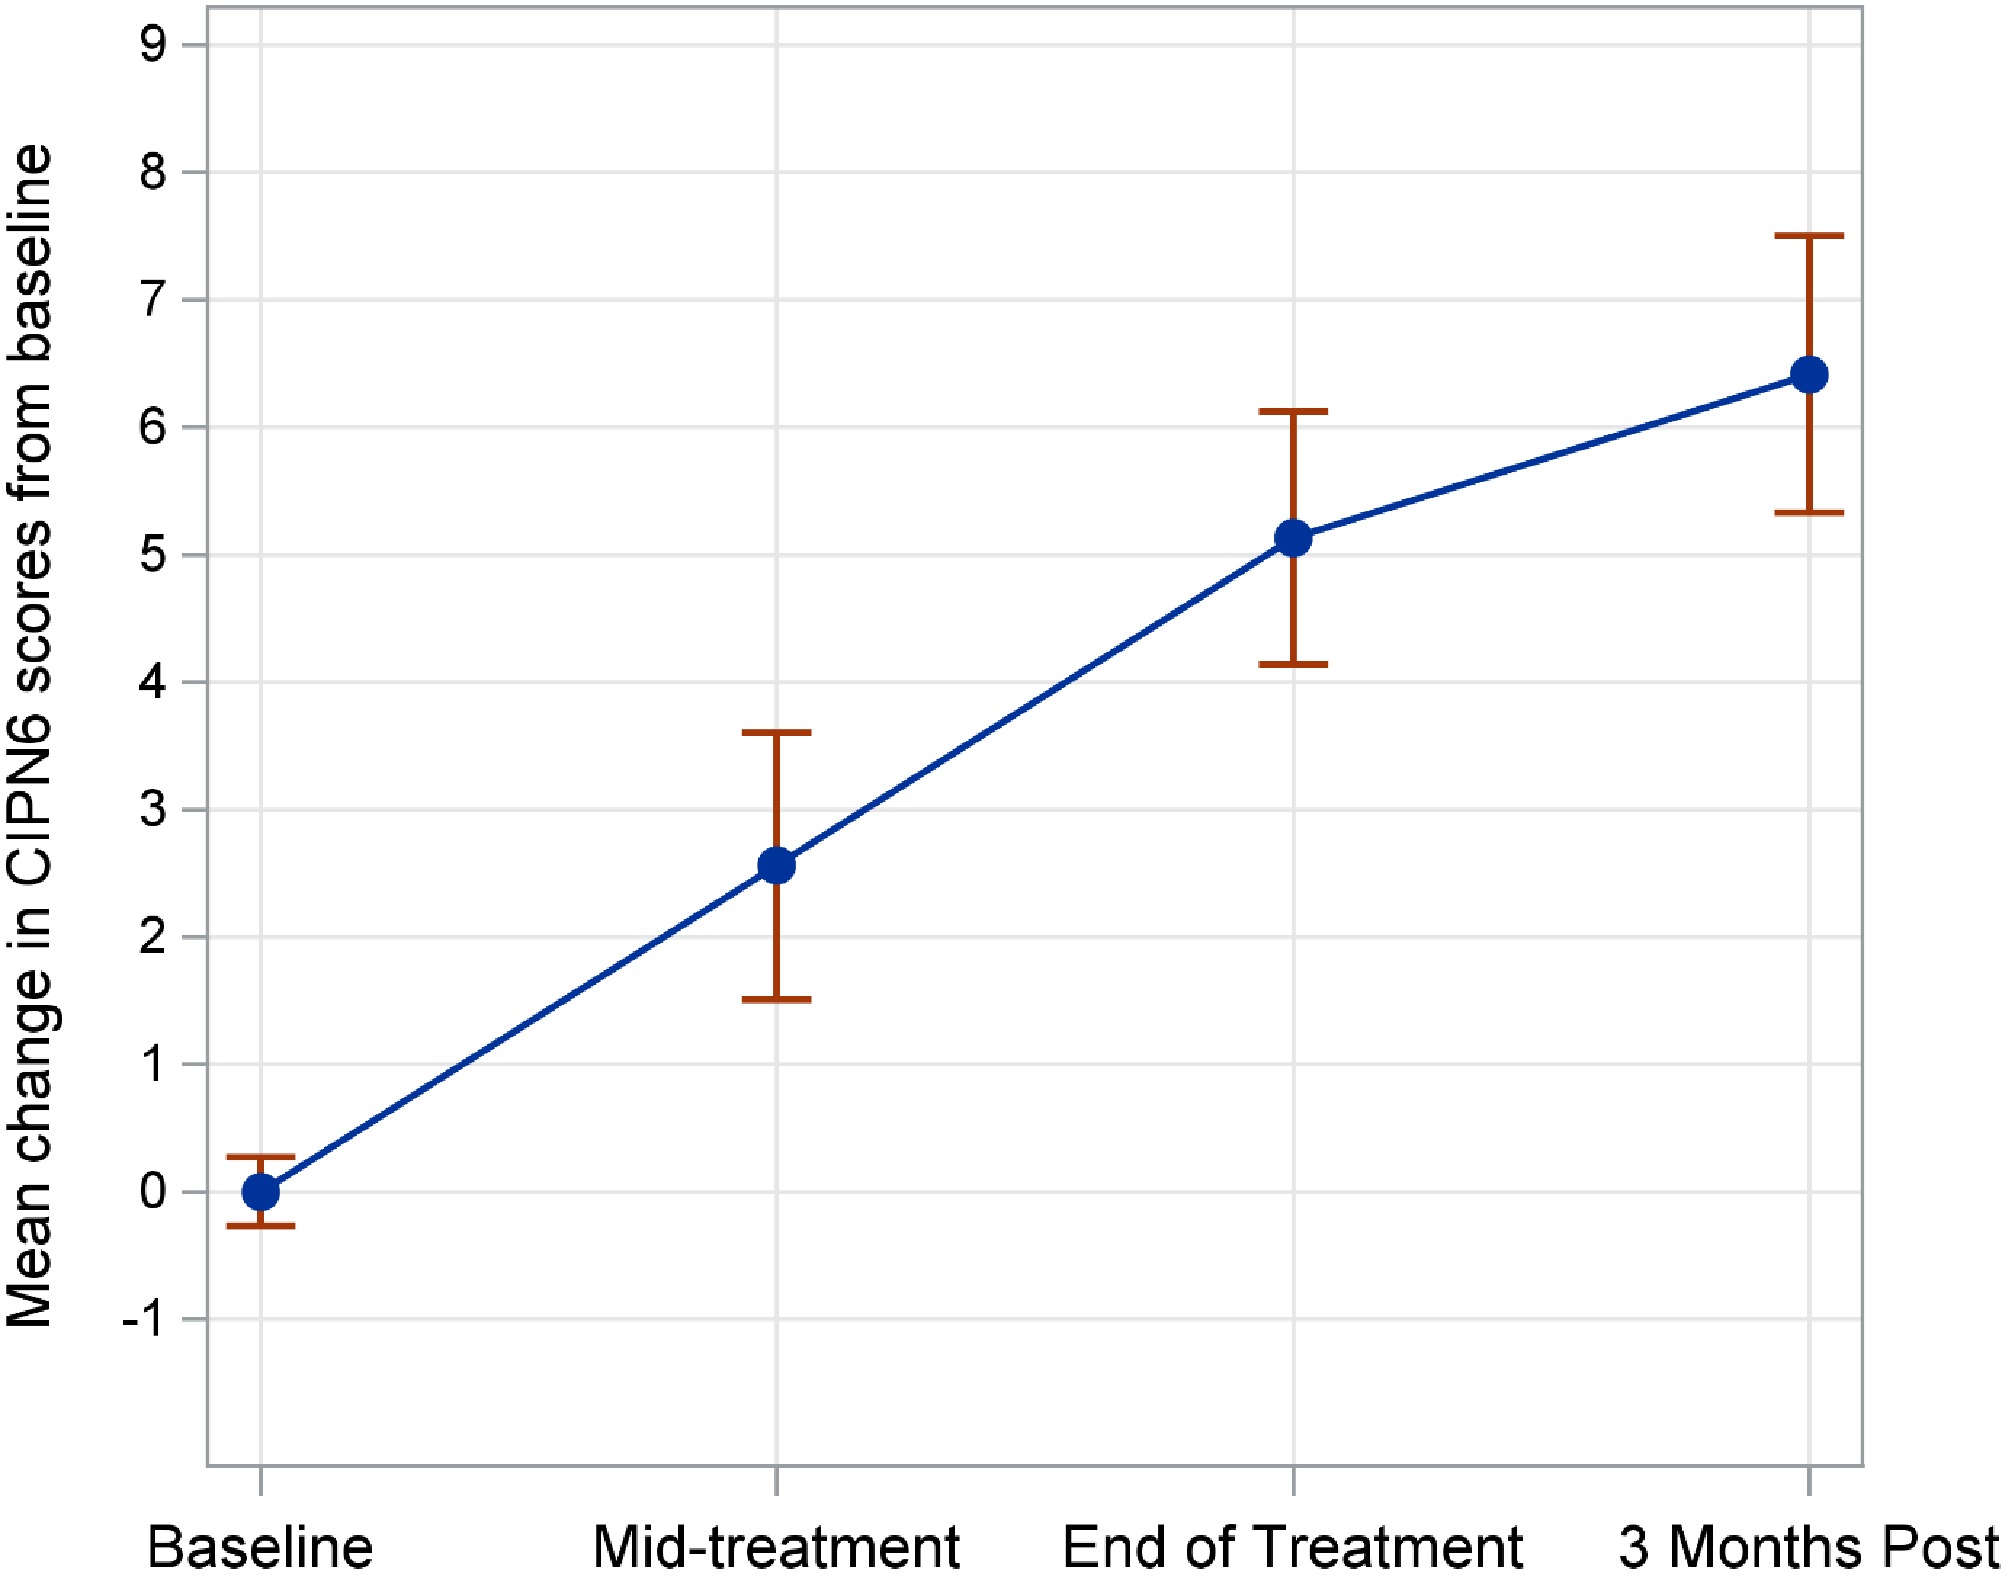
Figure 2.
Mean change in CIPN6 scores from baseline.
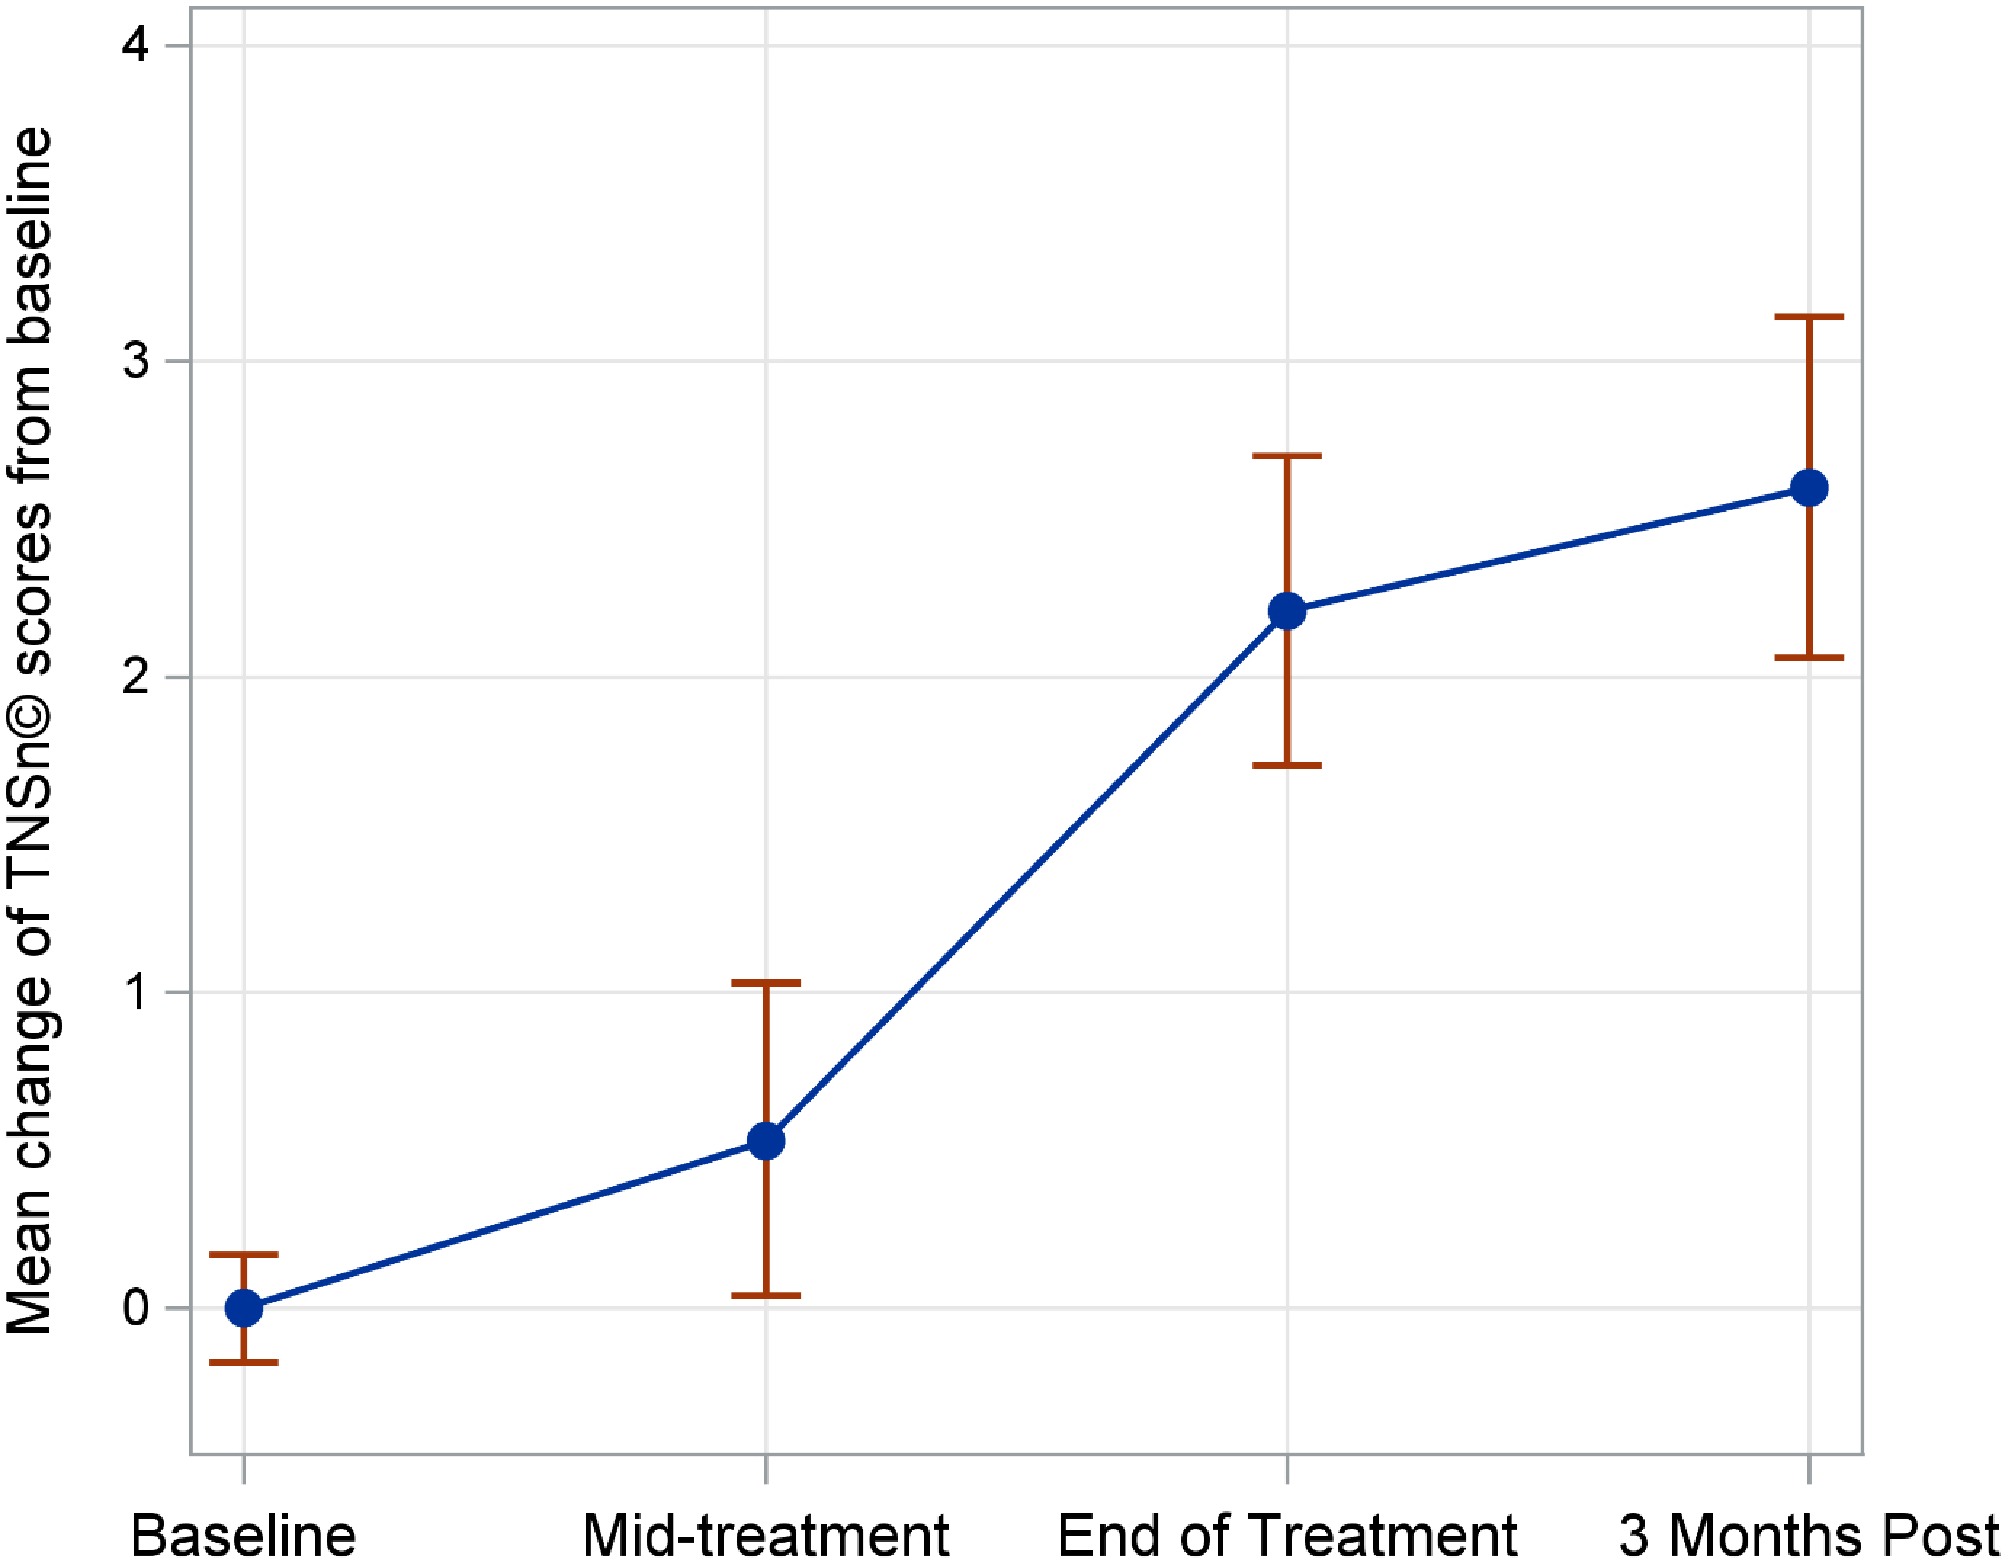
Figure 3.
Mean change in TNSn© scores from baseline.
A small subset of participants had relatively elevated baseline values (maximum 49.4 pg/mL) (Fig. 4).
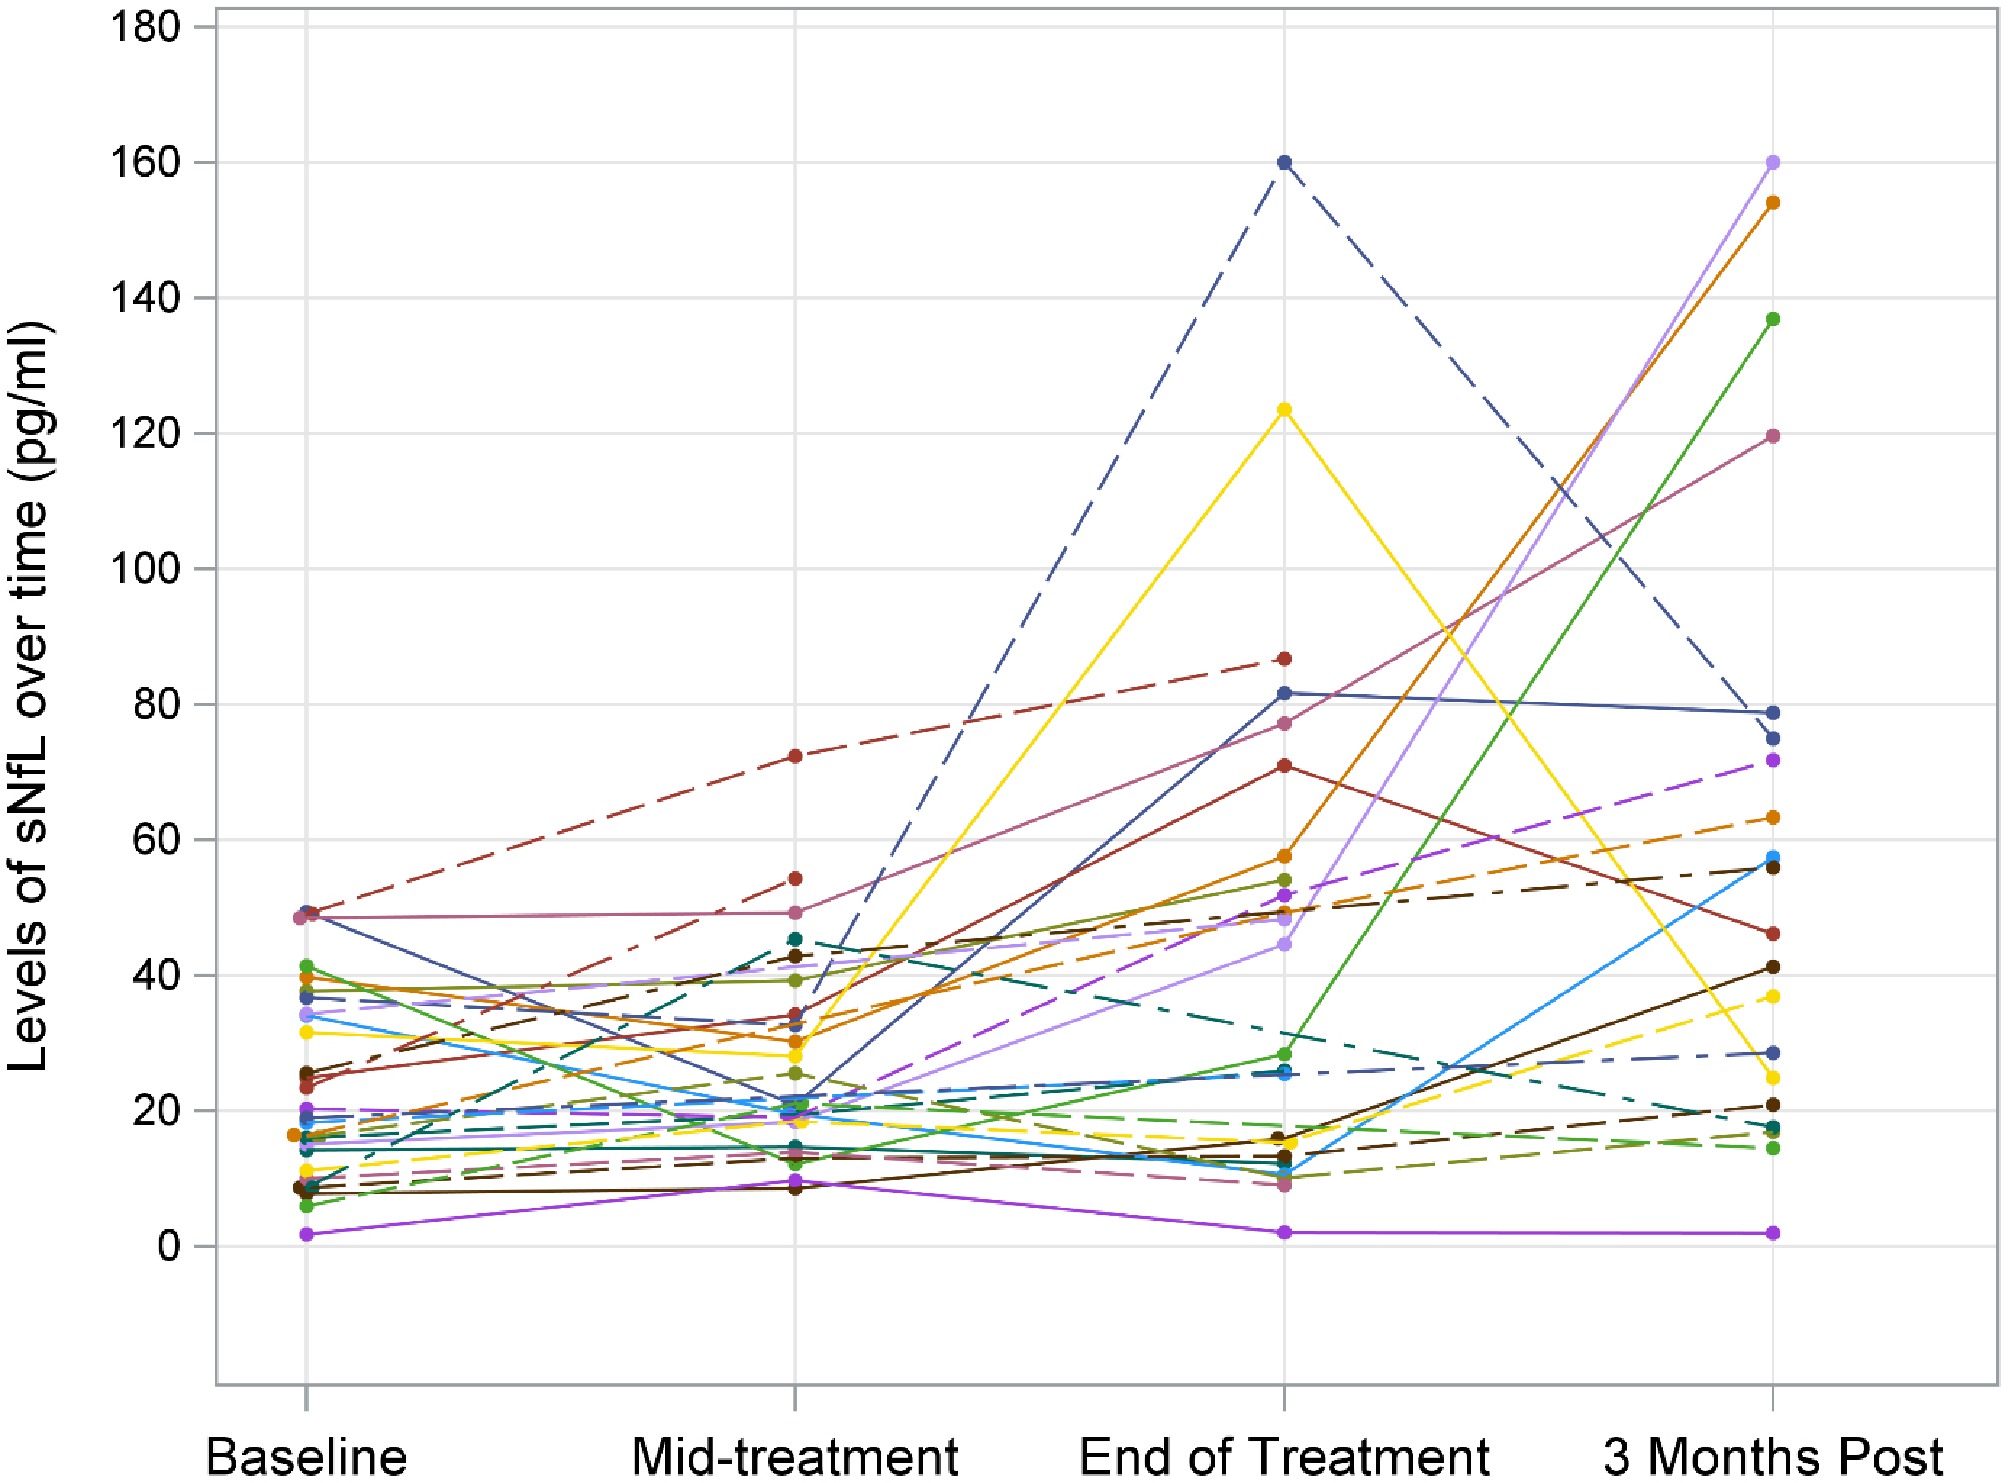
Figure 4.
sNfL individual values by timepoint.
At the 3-month follow-up, 18 of the 28 enrolled participants provided data. The reduced number reflects a combination of rescheduled clinic visits, patients lost to follow-up or choosing surveillance closer to home, and clinical deterioration that precluded sample collection. Further, 3-month sNfL values were significantly and moderately correlated with 3-month TNSn© (r = 0.51, p = 0.04) and CIPN6 scores (r = 0.58, p = 0.01). The LMM analysis also suggested a significant association of sNfL with TNSn© and CIPN6 scores after controlling for age, sex, race, and oxaliplatin cumulative dose. Specifically, after controlling for covariates, every one-unit increase in TNSn© score was associated with a 4.1 pg/mL increase in sNfL (p = 0.0137), while every one-unit increase in CIPN6 score was associated with a 2.0 pg/mL increase in sNfL (p = 0.0114). Taken together, these data provide evidence of sNfL responsiveness and convergent validity (correlation with similar measures) as an objective measure of oxaliplatin-induced CIPN.
-
In a small sample of patients who were receiving oxaliplatin to treat colorectal cancer, we showed that a serum-based biomarker, sNfL, is a responsive and valid indicator of worsening CIPN over time. Our results are consistent with results from other published studies demonstrating that rising sNfL values correspond to increases in validated subjective and objective CIPN measures in studies of chemotherapy-induced neurotoxicity caused by varied drug types[36−38,45−48]. Also, there was a larger range in sNfL score from baseline to the 3-month time point, suggesting that this biomarker measure will likely be more sensitive to detect subtle changes in neurotoxicity when compared to both the TNSn© and the CIPN6. Our findings are consistent with prior reports demonstrating rising blood sNfL with neurotoxic chemotherapy and associations with clinical neuropathy. For example, a prior study reported that sNfL increases with cumulative oxaliplatin and correlates with CIPN severity[42], and more recent observational studies[36,38,46,48] similarly observed treatment-related sNfL increases across taxanes and platinums. Differences across studies in absolute values and suggested thresholds likely reflect variation in assay methods, sampling schedules, patient age/comorbidities, and definitions of neuropathy; these differences highlight the need for assay standardization and larger multisite studies to establish generalizable cut-points.
Another advantage of using a biomarker to quantify CIPN is that it is easily obtained using a simple serum collection, does not require use of specialized neurotoxicity examination skills, and will not be subject to placebo response if used as a primary outcome measure in intervention trials. However, there are notable drawbacks. At this time, routine sNfL testing is not available in hospital laboratories, and samples must be processed in an outside laboratory, either through a basic science laboratory in a university setting, or through a commercial laboratory, and results can take weeks to become available. sNfL could be easily used as a primary outcome measure in future CIPN intervention studies because specimens can be frozen and then processed in batches. However, at this time, sNfL testing cannot be used to provide real-time information to guide chemotherapy dosing at the point-of-care.
Given the promise of sNfL biomarkers as an indicator of underlying mechanisms of oxaliplatin-associated axonal injury, future research is warranted to expand validation research to larger cohorts and to evaluate the value of sNfL to proactively identify patients who may be at the highest risk of developing severe and protracted CIPN so that interventions to mitigate chronic and debilitating CIPN can be used proactively. Further, collaboration with industry partners is needed to develop point-of-care methods for obtaining sNfL measures within routine clinical settings.
Although our data show responsiveness and convergent validity, there is not yet an established, universally accepted cut-point for clinically meaningful sNfL change in oxaliplatin-treated patients. Prior pilot work suggests candidate values (e.g., an increase ≈36 pg/mL associated with higher CIPN probability)[36], but these need replication and assay harmonization across platforms. Therefore, sNfL has the potential to serve as an objective monitoring outcome measure in clinical trials (to detect treatment-related change in axonal injury), and as an exploratory predictive biomarker in prospective studies where baseline and early-treatment samples are collected for prediction modeling. Definitive clinical cut-offs, age-adjusted reference ranges, and percent change thresholds should be established in larger, multi-site cohorts.
Strengths of this study include the longitudinal design, robust neurotoxicity phenotyping using validated subjective and objective measures, and excellent assessment fidelity due to the use of highly trained and consistent nurse assessors. This study also has several limitations. First, the findings are mainly descriptive in nature and only provide clues regarding the predictive relationships between sNfL and long-term neurotoxicity outcomes. Regression analyses to assess predictive relationships between baseline or EOT values and 3-month outcomes were not conducted due to the small sample size. Further, only patients receiving oxaliplatin were included in the sample, limiting generalization of the findings to neurotoxicity caused by other neurotoxic drugs (e.g., taxanes, cisplatin, vincas). Larger longitudinal studies are needed to expand upon these findings, with inclusion of patients receiving other types of neurotoxic chemotherapy drugs, and sNfL should be collected alongside other validated measures in future intervention studies to show that values drop when neurotoxicity lessens. Lastly, collaboration with industry/engineering partners is critical to develop point-of-care technology allowing real-time sNfL data to become available during routine oncology chemotherapy clinical visits. Without this technological advancement, sNfL-based clinical decision-making will not be possible.
-
Our study results suggest that sNfL has the potential to provide highly valid and sensitive information as a primary outcome measure in future CIPN trials. Based on current evidence, sNfL might be useful as a monitoring biomarker in clinical trials, to be used alongside PROMs and clinician measures. It also shows promise as a predictive biomarker (early increases predicting later CIPN), but this use requires larger, prospective validation with pre-specified thresholds and adjustment for confounders (age, comorbidities, baseline sNfL). Future validation studies are needed before sNfL can be recommended as a sole outcome measure in clinical trials.
We would like to acknowledge the patients who participated in this study. Jennifer Kreider, BSN, RN is acknowledged for her work to recruit and collect data.
-
The study was conducted in accordance with the Declaration of Helsinki, and the protocol and all procedures were reviewed and preapproved by the University of Alabama at Birmingham (UAB) Institutional Review Board (IRB-300007934-021) and initially approved on November 1, 2021 (see two sequential approval letters spanning 2021 to 2027). Written informed consent for participation was obtained from all subjects involved in the study. The authors did not use AI in the preparation of this manuscript.
-
The authors confirm their contributions to this study as follows: study conception and design: Smith EML, Alberti P; data collection: Carlee J, Hornsby E, Kreider J; analysis and interpretation of results: Smith EML, Alberti P, Daniel M, Li P, Odii C, Haamankuli H; draft manuscript preparation: Smith EML, Alberti P, Carlee J, Hornsby E, Kreider J, Daniel M, Li P, Odii C, Haamankuli H. All authors reviewed the results and approved the final version of the manuscript.
-
The dataset generated and analyzed in the current study is available from the corresponding author upon reasonable request.
-
None of the authors have a conflict of interest to declare.
-
accompanies this paper online at: https://doi.org/10.48130/ejcc-0026-0012.
- Supplementary Table S1 (a) TNSn© scoring. (b) cIPN6 Scoring.
- Copyright © 2026 by the author(s). European Journal of Cancer Care by Maximum Academic Press on behalf of John Wiley & Sons Ltd. This is an open access article under the terms of the Creative Commons Attribution License, which permits use, distribution and reproduction in any medium, provided the original work is properly cited.
-
About this article
Cite this article
Smith EML, Daniel M, Li P, Carlee J, Odii C, et al. 2026. The promise of serum neurofilament light as a future primary outcome target in clinical trials testing oxaliplatin-induced peripheral neurotoxicity interventions. European Journal of Cancer Care 2026: e009 doi: 10.48130/ejcc-0026-0012 
The promise of serum neurofilament light as a future primary outcome target in clinical trials testing oxaliplatin-induced peripheral neurotoxicity interventions
- Received: 30 June 2025
- Revised: 24 April 2026
- Accepted: 23 June 2026
- Published online: 24 August 2026
Abstract: Chemotherapy-induced neurotoxicity (CIPN) poses a major health risk for cancer survivors. CIPN is experienced by nearly all patients (94%) who receive oxaliplatin, but in varying degrees of severity and chronicity. While we know that CIPN is pervasive and disabling, no effective preventive interventions for high-risk patients exist. Future intervention research will benefit from identification of objective clinical biomarkers that can detect clinically important changes in CIPN resulting from an effective intervention. The purpose of this pilot study was to validate a promising CIPN biomarker, serum neurofilament light chain (sNfL), for use as an objective outcome measure in future oxaliplatin-induced CIPN prevention trials. The study objective was addressed using a prospective, longitudinal, descriptive design. Eligible patients had stage II-III colorectal cancer, were ≥ 18 years of age, had a Karnofsky performance status score ≥ 70, and were scheduled to receive oxaliplatin-containing adjuvant treatment regimens. At each of four timepoints, CIPN was assessed using the Total Neuropathy Score-Nurse (TNSn©), and a validated patient-reported outcome measure, the CIPN6. To quantify sNfL levels, we collected 5 mL of whole blood at each timepoint. Twenty-eight patients participated in the study; most were male (n = 19, 67.9%) and Caucasian (n = 22, 78.6%). There were statistically significant changes over time across all three CIPN measures (TNSn©, CIPN6, sNfL). sNfL values were significantly and moderately correlated with 3-month TNSn© (r = 0.51, p = 0.04) and CIPN6 scores (r = 0.58, p = 0.01). These data provide preliminary evidence of sNfL validity as an objective measure of oxaliplatin-induced CIPN.