










-
Efferocytosis is a specialized form of phagocytosis. The term refers specifically to the selective removal of apoptotic cells (ACs) by professional phagocytes, e.g., macrophages and dendritic cells, as well as by certain non-professional phagocytes, including epithelial cells. Unlike classical phagocytosis, efferocytosis generally prevents the initiation of inflammation, promotes immune tolerance, and preserves tissue homeostasis[1,2]. Henson introduced the word 'efferocytosis' in 2003 to highlight distinct physiological and immunological features compared with conventional phagocytosis[3]. The underlying concept traces back to Metchnikov's seminal observations[4]. Over the past two decades, efferocytosis has come to be recognized as a terminal clearance step and a critical regulatory switch. This switch determines whether inflammation resolves or persists and whether tissue repairs or moves toward fibrosis[5]. Under physiological conditions, efferocytosis prevents secondary necrosis and supports tissue repair[6]. When efferocytosis becomes impaired, apoptotic cells accumulate and trigger or amplify pathological responses. This mechanism has been demonstrated across a range of diseases[7]. Defective efferocytosis promotes necrotic core expansion in atherosclerotic plaques and worsens post-infarction remodeling and cardiac dysfunction[8,9]. In the nervous system, poor clearance of dying neurons exacerbates tissue damage and accelerates functional decline[10]. In autoimmune disease, impaired efferocytosis facilitates the release of self-antigens and disrupts immune tolerance[11]. Within the tumor microenvironment, defective efferocytosis establishes an immunosuppressive niche that fosters immune evasion and tumor progression[12,13]. These systemic consequences highlight the indispensable role of efferocytosis in maintaining homeostasis and underscore the function of efferocytosis as a central regulatory hub in the pathogenesis, progression, and therapeutic targeting of multiple diseases[14]. From a translational perspective, therapeutic strategies targeting efferocytosis have shown early clinical promise. Blockade of the CD47-SIRPα pathway, for example, has entered clinical trials for cancer immunotherapy[15,16]. Nevertheless, systematic evaluation of efferocytosis in the key area of liver fibrosis remains relatively limited.
Liver fibrosis is a key pathological process in the progression of chronic liver disease, affecting 0.7% to 25.7% of the global population[17], with advanced fibrosis representing around 3.5% and cirrhosis 1.2%[18,19]. Despite gaining mechanistic insights over the past forty years, no antifibrotic therapy has secured regulatory approval. Fibrosis in early stages may be reversible, yet it is typically symptomless and not diagnosed, whereas cirrhosis suggests a severe drop in clinical health[20]. Importantly, the 26% fibrosis reversal rate seen with resmetirom in clinical trials highlights the critical need to understand fibrogenic mechanisms[21]. Since the 1980s, hepatic stellate cells (HSCs) have been recognized as the main source of the extracellular matrix (ECM)[22], LF has been identified as a responsive wound healing process to persistent injury[23]. Recent progress in single-cell and spatial omics has allowed for a systematic analysis of cell-cell interactions and fibrogenic mechanisms specific to certain etiologies, demonstrating that LF is a complex multicellular process, guided by hepatocyte damage, macrophage activation and polarization, HSCs transdifferentiation, and the coordinated participation of other immune and mesenchymal cell types[24]. Extensive research has linked hepatocyte apoptosis to fibrosis[25]. Efferocytosis represents the main route for clearing ACs, and the functional consequences of efferocytosis deserve close examination. This raises a central question: what role does efferocytosis, the primary mechanism for clearing ACs, actually play in this process? A protective repair mechanism, or a driver of fibrosis? Available evidence suggests that efferocytosis exerts dual mechanisms. One potential mechanism involves the clearance of ACs to prevent release of damage-associated molecular patterns (DAMPs); defects or a shift towards inflammatory cell death types like necroptosis, necrosis, or ferroptosis might contribute to fibrosis[26]. Alternatively, pro-fibrotic efferocytosis mediated by transforming growth factor-beta (TGFβ) and pro-inflammatory non-apoptotic cell death mediated by DAMPs may coexist and synergize to enhance fibrogenesis[27,28]. Many gaps remain in current knowledge regarding the role of efferocytosis in the pathogenesis of LF. Several existing reviews have addressed apoptosis in liver fibrosis or macrophage biology in chronic liver disease[29,30]. However, no review to date has focused specifically on efferocytosis in the context of liver fibrosis or has systematically described the dual role of efferocytosis in the progression and resolution of liver fibrosis. Here, our review has three distinctive features. First, we integrate recent discoveries on how efferocytosis dysfunction drives fibrosis through macrophage-intrinsic pathways and direct HSC engulfment. Second, we highlight the dual role of efferocytosis: worsening fibrosis during chronic injury and promoting resolution after injury removal. Third, we point out current knowledge gaps and therapeutic opportunities for targeting efferocytosis in liver fibrosis and propose important topics for future studies, including therapeutic applications.
-
Efferocytosis, a process crucial for immune homeostasis, involves multiple regulated steps like the recognition, engulfment, and degradation of apoptotic cells, each governed by distinct signaling molecules[31,32]. Initially, in the recruitment phase, dying cells release soluble 'find-me' signals that help phagocytes migrate via specific receptors. These signals include nucleotides ATP and UTP, which engage the purinergic receptor P2Y2[33], lysophosphatidylcholine (LPC) attaches to G protein-coupled receptor 132[34], sphingosine-1-phosphate engages sphingosine-1-phosphate receptors[35], and C-X3-C motif chemokine ligand 1 binds with C-X3-C motif chemokine receptor 1[36]. Additional cues such as thrombospondin 1, Annexin A1 (ANXA1), and ribosomal protein S19 (RPS19) are involved, with ANXA1 and RPS19 distinctively drawing mononuclear phagocytes while curbing neutrophil entry to prevent inflammatory clearance[37]. Conversely, endothelial monocyte activating polypeptide II and tyrosyl-tRNA synthetase are still considered potential candidates because there is not enough evidence for direct phagocyte guidance[38]. Interference with this signaling system may hinder efferocytosis, leading to secondary necrosis. During the recognition phase, ACs expose phosphatidylserine (PS), the typical 'eat-me' signal, by caspase-induced flippase inactivation[39], at which point PS is recognized directly by phagocyte receptors (TIM4, BAI1)[40] or indirectly via bridging molecules GAS6 and MFGE8[41] that interact with TAM family receptors (TYRO3, AXL, MerTK)[42]. Calreticulin and LPC signals also contribute to promoting engulfment[43]. Alongside pro-phagocytic signals, healthy cells emit a 'don't-eat-me' CD47 signal, which binds to phagocyte SIRPα to summon src-homology region 2 domain phosphatase-1/2 phosphatases and inhibit phagocytosis[44]. Under normal and pathological conditions, the balance between 'eat-me' and 'don't-eat-me' signals plays a critical role in determining efferocytosis efficiency.
The third stage is the internalization phase, involves receptor engagement activating the rac family small GTPase 1 (RAC1) via two routes: the GULP adaptor linked to LDL receptor related protein 1 and STABILIN2, or the TRIO-RHOG-ELMO1-DOCK180 pathway[45,46]. Calcium influx through the mechanosensitive channel PIEZO1 activates RAC1[47], which subsequently recruits WASP, an actin nucleation-promoting factor, and WAVE regulatory complex effectors to activate the actin-related protein 2/3 complex[48], initiating actin nucleation and polymerization to create the phagocytic cup. Whereas the closure of the cup necessitates RAC1 inactivation through GAPs activated by phosphatidylinositol-3,4,5 trisphosphate to halt actin assembly, simultaneously enabling actin depolymerization to work together with dynamin 2-driven membrane fission, thus cutting the vesicle to form a new phagosome[49,50]. In the final digestion phase, newly formed phagosomes mature through the sequential actions of RAB5 and RAB7[51], eventually fusing with lysosomes to create phagolysosomes where acidic hydrolases break down apoptotic cargo[52]. Alternatively, LC3-associated phagocytosis speeds up this process via phosphatidylinositol 3-kinase catalytic subunit type 3, RUBICON, and reactive oxygen species produced by nicotinamide adenine dinucleotide phosphate oxidase 2 (NOX2)[53]. Catabolic processing, beyond just clearance, initiates metabolic reprogramming: glycolysis-produced lactate activates a signaling cascade with protein kinase cAMP-activated catalytic subunit alpha, protein kinase AMP-activated catalytic subunit alpha 1, and SIRTUIN1, fostering the growth of pro-reparative macrophages[54]. ACs-derived arginine is broken down through ARG1/ODC into putrescine, which maintains RAC1 activation for ongoing efferocytosis[45]. These insights deepen our understanding of the removal of apoptotic cells and stress its therapeutic relevance in LF. Clarifying how efferocytosis is dysregulated in these pathological situations might open up new avenues for LF therapy (Fig. 1).
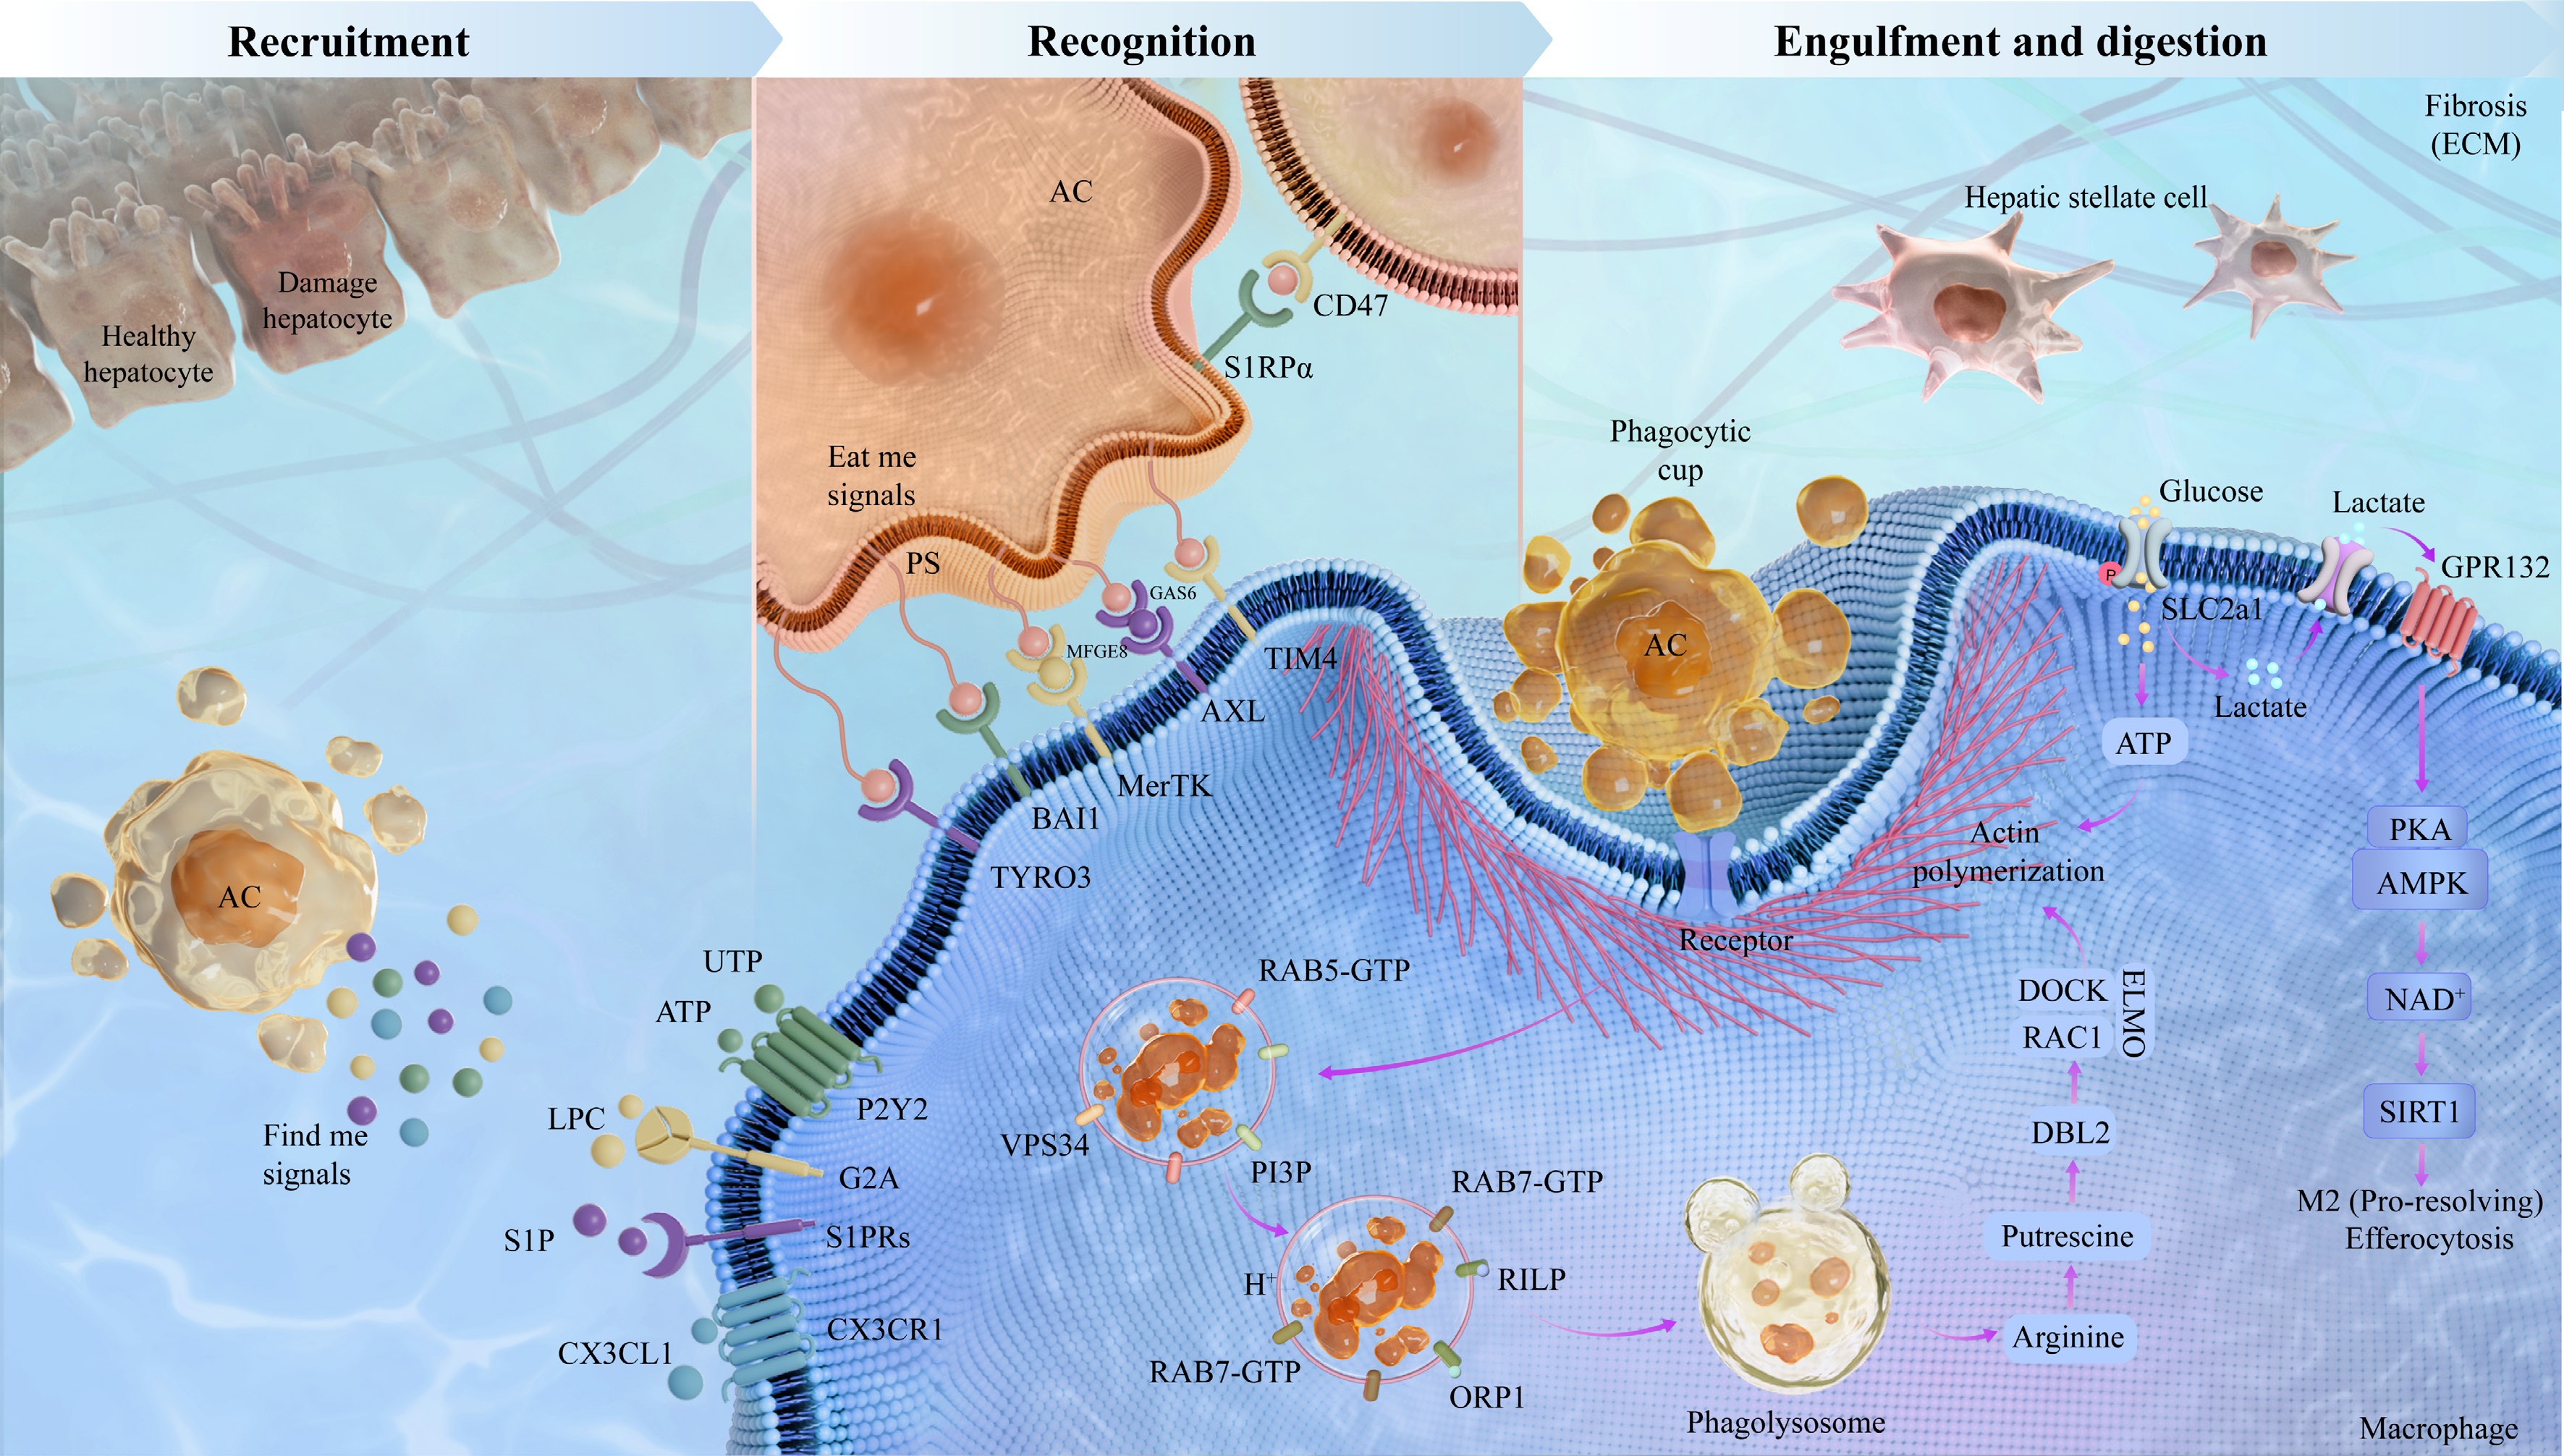
Figure 1.
The sequential stages of efferocytosis in liver fibrosis. Efferocytosis is a multifaceted process divided into four phases: the recruitment stage, the recognition stage, and the engulfment and digestion stage. In the recruitment stage, apoptotic hepatocytes release soluble mediators LPC, S1P, ATP, UTP, and CX3CL1 to recruit macrophages. During the recognition stage, macrophages recognize apoptotic hepatocytes through interactions between 'eat me' signals, PS, and phagocyte surface receptors including MerTK, AXL, TIM, BAI1, TYRO3, and STABILIN. Healthy cells display the 'don't-eat-me' signal CD47; this classical protective signal is often overexpressed under conditions associated with defective clearance of apoptotic cells, and blockade of the CD47-SIRPα axis has been exploited in cancer therapies and atherosclerosis. In the engulfment and digestion stage, macrophages efficiently digest and degrade engulfed apoptotic hepatocytes along with cellular contents. This stage exerts anti-inflammatory effects through phagolysosomal degradation of ACs, a process involving RAB7-GTP, RILP, and VPS34 that generates metabolites and pro-resolving IL10 and TGFβ signals. Such factors promote M2 macrophage polarization and TGFβ release, subsequently suppressing HSCs activation, enhancing ECM degradation, and mitigating fibrosis.
-
Interestingly, efferocytosis serves a dynamic and reciprocal regulatory role in liver fibrosis. In a healthy state, phagocytes efficiently eliminate ACs to suppress inflammation and the activation of HSCs, offering protection. Nonetheless, ongoing injury causes efferocytosis to become dysregulated, either excessively or inadequately, resulting in phagocyte malfunction, increased matrix buildup, and a transition from repair to fibrosis (Table 1).
Table 1. Core regulatory factors and mechanisms of efferocytosis in liver fibrosis.
Regulator Targets Mechanisms Key effects Intervention strategies Ref. Protective role MerTK NLRP3 activation inhibits MerTK-mediated efferocytosis Reduces DAMPs release and promote
fibrosis resolutionMCC950 [57,58] GPNMB Ly6C+ monocytes switch to restorative macrophages via ERK for MMP resolution Matrix degradation, HSCs inactivation, scar remodeling, and fibrosis resolution Liposome-induced phagocytosis [59] MerTK Suppresses pro-fibrotic factors, upregulates MMPs, and promotes ECM degradation Promotes matrix degradation and reduces inflammation Enhance MerTK function [60] TREM2 TREM2 expression in LAMs promotes efferocytosis and collagen degradation Apoptotic hepatocytes clearance and HSCs inactivation, fibrosis resolution TREM2 agonists [67] CD47, SIRPα Blocks CD47-SIRPα to promote macrophage clearance of necroptotic hepatocytes Inhibits HSCs activation and reduces liver fibrosis Anti-CD47 antibody [70] MerTK, GAS6 ADAM17-mediated MerTK cleavage releases soluble fragment that blocks GAS6 Inhibits HSCs activation and
reduces liver fibrosisEnhance MerTK function [71] CD68 Macrophage engulfment of apoptotic cells upregulate MMP3, MMP8, and MMP9 Fibrosis reversal, septa fragmentation, and liver architecture restoration Roux-en-Y anastomosis [72] TIM4 Restores TIM4 mediated efferocytosis and increases IL10 Suppresses HSCs activation, and reverses fibrosis progression TIM4 restoration [73] TIM4 Inhibits AKT1 and ROS mediated mitophagy axis in KCs, reducing TGFβ1 secretion Reverses fibrosis, restores architecture, and attenuates post-LT fibrosis TIM4 mAb [74] Pathological role αvβ3 CCN1 via αvβ3 bridges ACs to macrophages, triggering efferocytosis and TGFβ1 Activates HSCs and induces myofibroblast transdifferentiation Block CCN1-αvβ3 binding [27] MerTK Increases MerTK expression via rs4374383 GG/GA, and enhances HSCs procollagen Activates HSCs and fibrosis progression MerTK inhibitors [81] TREM2+ macrophage TREM2+ SAMs highly express SPP1 promotes type I collagen production Promotes scar formation and exacerbates liver fibrosis Osteopontin neutralization [82] AXL Phosphorylates SMAD3 via AXL, and upregulates PAI1, MMP9, SNAIL, and TGFβ1 Activates HSCs and ECM deposition AXL inhibitors [85,86] GAS6 GAS6 impairs β-oxidation and upregulates inflammatory cytokines Recruitments of macrophages drives liver fibrosis progression BGB324 [87] NADPH oxidase Induces apoptotic body phagocytosis, NADPH oxidase activation, and ROS production Activates HSCs and extracellular matrix deposition ROS scavenger [89] FasL Apoptotic body engulfment by KCs upregulate FasL and TNFα Induces inflammation and activates HSCs Gadolinium chloride [90] αvβ3 Enhances apoptotic body phagocytosis and activates NF-κB pathway Activates HSCs and increase production of TGFβ and collagen I Galectin-3 inhibition [91] CD36 CD36 regulated by FABP7 controls KCs phagocytosis and MCP1, TGFβ production Activates HSCs and fibrosis progression FABP7 modulation [92] Protective role: efficient efferocytosis promotes inflammation resolution and fibrolysis
-
Multiple cell types are involved in resolving fibrosis, notably macrophages that facilitate resolution and degrade the extracellular matrix. Their pro-resolving ability is significantly reliant on efficient efferocytosis. By clearing ACs, efferocytosis gets rid of inflammatory triggers, leading to a change in macrophage phenotype towards a pro-repair state, which increases matrix metalloproteinase activity to degrade ECM and further modulates HSCs activation.
Promotion of macrophage phenotypic switching
-
Efferocytosis plays a vital role in shifting macrophages from a fibrosis-inducing to a repair-promoting phenotype. Notably, when macrophages consume apoptotic hepatocytes, they show heightened mTORC1 activity and mitochondrial calcium release, which encourages their shift to a pro-resolving state, while defective efferocytosis hinders this transformation[55]. For example, a lack of the NOX2 catalytic subunit GP91phox causes a decrease in MerTK and TIM4 phagocytic receptors, leading to the buildup of ACs and hindering the shift of macrophages from a pro-inflammatory to a tissue-repair phenotype, worsening the severity of the disease[56]. Moreover, the activation of the NLRP3 inflammasome hinders liver regeneration by disrupting MerTK-mediated efferocytosis and preventing macrophages from polarizing to the pro-repair Ly6Clow phenotype[57]. Remarkably, the NLRP3 inhibitor MCC950 reinstates phagocytic clearance capacity and facilitates liver regeneration after hepatectomy[58]. This discovery has important consequences for liver fibrosis: MCC950 aids in the removal of ACs by restoring MerTK mediated efferocytosis, which reduces the release of DAMPs and consequently diminishes inflammatory signaling before HSCs activation. Simultaneously, macrophage polarization toward the pro-repair Ly6Clow phenotype may be encouraged. The Ly6Clow macrophage population shows elevated levels of MMP9, MMP12, IGF1, and the phagocytosis-related gene GPNMB. It relies on ERK signaling to drive phagocytic activity that helps break down ECM components during the resolution of fibrosis[59,60]. Therefore, MCC950 aids in liver regeneration and presents a possible therapeutic target for liver fibrosis, especially by addressing the phenotypic transition driven by efferocytosis[61]. Besides, the expression of the efferocytosis receptor TREM2 is closely related to the protective functions of macrophages. A lack of this molecule in myeloid cells leads to increased fibrosis[62,63]. Within NASH models, macrophages that are TREM2 positive grow and position themselves in collagen scar zones, contributing to anti-fibrotic actions[64]. Likewise, macrophages expressing MerTK offer protective effects, with the transfer of these cells leading to higher serum HDL levels, a reduction in circulating T cells, and decreased fibrosis severity in experimental liver disease[65].
Macrophage responses to apoptotic cells: anti-fibrotic functions in the injured liver
-
Apoptosis of hepatocytes contributes to the progression of LF, and efferocytosis is an essential protective mechanism that clears ACs to prevent secondary necrosis and control fibrogenesis. The effective phagocytosis by macrophages blocks the release of mitochondrial DAMPs from hepatocytes, which hinders the progression of fibrosis[66]. Maintaining the integrity of efferocytic receptors is vital for clearance functions, since TREM2 deficiency reduces macrophage ability to engulf dying liver cells and hastens the development of liver fibrosis[67−69]. Similarly, the upsurge of CD47 on necroptotic liver cells and the heightened SIRPα on macrophages obstruct phagocytic clearance; notably, interfering with the CD47-SIRPα pathway restores macrophage clearance and mitigates fibrosis linked to NASH[70]. With the onset of efferocytosis, macrophages increase the production of several pro-resolving and anti-fibrotic agents. In the progression of MASH-related liver fibrosis, TREM2-positive macrophages show higher levels of MMPs linked to fibrosis resolution, thus augmenting the activity that degrades collagen[67]. A negative feedback regulatory mechanism is activated through ADAM17-mediated cleavage of MerTK, which releases a soluble ectodomain that binds to GAS6 and inhibits GAS6-induced TGFβ1 production[71]. Functionally, Macrophages with MerTK expression ease fibrotic conditions in LF by suppressing pro-fibrotic elements (e.g., COL1A1 and FN, the cytokine TNF), and the lipid metabolism regulator PPARγ[65].
Resolution-phase efferocytosis: dynamic mechanisms driving fibrosis regression
-
Beyond the protective functions discussed above, efferocytosis also drives fibrosis regression. This occurs when the underlying injury is removed or when pathological efferocytosis is therapeutically blocked. Reversing cholestatic liver fibrosis begins with restored bile flow, which induces apoptosis of activated cholangiocytes. Macrophage uptake of the apoptotic cholangiocytes upregulates the expression and activity of MMP3, MMP8, and MMP9. Degradation of the extracellular matrix by the three metalloproteinases promotes fibrosis reversal[72]. Separately, restored TIM4 expression in macrophages following clearance of apoptotic hepatocytes reprograms the macrophages to secrete IL10 activate the IL10 receptor on HSCs, and suppress HSCs' pro-fibrotic activation[73]. Another line of evidence shows that TIM4 suppresses AKT1-mediated reactive ROS production. Suppression of ROS production limits PINK1, PARKIN, and LC3-II/I dependent mitophagy activation. The result is reduced secretion of the pro-fibrotic factor TGFβ1 from KCs[74]. In a distinct mechanical axis, macrophage PIEZO1 senses increased liver stiffness. PIEZO1 activation enhances efferocytic uptake (phagocytic index 40%), clears apoptotic debris, and promotes an IL10-producing phenotype, thereby driving fibrosis resolution[47]. Baoganning decoction suppresses liver fibrosis via 19α-hydroxyasiatic acid-mediated IDO1 inhibition, which abrogates IDO1-driven pro-fibrotic macrophage efferocytosis and reduces TGFβ1 production and HSCs activation[75]. Phocaeicola dorei ameliorates cholestatic fibrosis by restraining neutrophil degranulation and infiltration, restoring CX3CL1/CX3CR1 chemokine balance, and directly blocking macrophage efferocytosis of apoptotic neutrophils[76].
To sum up, the resolution of fibrosis depends on three key cellular processes: enhanced survival of hepatocytes, macrophage reprogramming to a pro-resolving state, and the apoptosis or inactivation of HSCs. Efferocytosis coordinates the interaction between multiple cell types, acting as a key point that connects the removal of dying liver cells to the activation of healing macrophage responses and the reduction of HSCs-induced fibrogenesis.
Pathological role of efferocytosis in HSCs activation and fibrosis progression
-
Unlike the protective role of effective efferocytosis, impaired efferocytosis disturbs the tissue repair equilibrium usually upheld by proper TGFβ secretion in normal conditions. As a result of this dysfunction, ACs gather in liver tissue, leading to secondary necrosis and the release of substantial amounts of DAMPs[77]. In this stage, liver macrophages maintain a pro-inflammatory state and excessively produce this cytokine, which directly activates HSCs and accelerates fibrosis progression[78]. Moreover, uncleared ACs influence stellate cells by emitting hedgehog ligands and osteopontin, or by sending signals through apoptotic bodies, potentially operating in three different ways: (1) serving as main influencers in settings where macrophages derived cytokine signaling are weak[79]; (2) collaborating with cytokine-driven HSCs activation to intensify fibrosis progression[80]; or (3) indirectly strengthening the fibrotic response by boosting the activation or transmission of this cytokine's signals within stellate cells[81]. Focusing again on the main problem of efferocytosis dysfunction: if the removal of apoptotic cells is truly hindered in the liver, what is the connection to the development of liver fibrosis? The primary mechanism involves the activation of HSCs by leftover apoptotic cell debris.
Macrophages' intrinsic pro-fibrotic signaling is triggered by efferocytosis dysfunction
-
The signaling pathways inherent to macrophages are crucial in this pathological process. Studies have shown that activating MerTK in macrophages leads to a pro-fibrotic secretome, which encourages the migration, proliferation, and survival of HSCs, while also increasing the expression of pro-fibrotic factors like TIMP1, TGFβ1, ACTA2, and COL1A1[82]. Genetic evidence supports the clinical importance of this signaling: NAFLD patients with the rs4374383 G>A variant in the MerTK locus show decreased hepatic MerTK mRNA expression, and have a considerably decreased incidence of liver fibrosis[83]. Single-cell transcriptomics has revealed a group of macrophages expressing TREM2, known as scar-associated macrophages (SAMs), which were originally thought to promote fibrosis. Despite SAMs having a gene expression signature similar to lipid-associated macrophages, including TREM2 and CD9, they express SPP1 at high levels, which encodes osteopontin, a protein that directly drives type I collagen production by HSCs[84]. Evidence for the pro-fibrotic function of SAMs includes: (1) elevated levels of SPP1[84]; (2) engagement with endothelial and mesenchymal cells through TNFRSF12A, PDGFR, and NOTCH signaling pathways, which enhance fibrosis[85]; and (3) global prevention of monocyte-to-macrophage conversion to minimize SAMs diminishes LF in mice. However, it must be noted that genetic tools to specifically deplete myeloid TREM2 without affecting other macrophage subsets are currently lacking. Therefore, the precise pro-fibrotic role of SAMs requires further validation[86]. In cirrhosis, AXL signaling kicks into gear and drives SLUG transcription, being a master switch for EMT. Alongside that, AXL partners with TGFβ to ramp up the production of α-SMA, collagen, and MMPs, all through a SMAD3-dependent pathway[87,88]. At ligand levels, GAS6-deficient animals in a steatohepatitis model showed less liver inflammation and fibrosis, along with lower TGFβ and collagen I expression[89]. Mito-DAMPs leaking from apoptotic liver cells are found at higher levels in the blood. These levels track closely with the degree of fibrosis, poor clearance of necrotic debris, and reduced uptake of dying cells. Beyond mitochondria, other DAMPs released from apoptotic cells that escape clearance may also drive HSCs activation; one class binds the P2Y14 receptor on hepatic stellate cells[90].
Efferocytosis of apoptotic bodies directly activates HSCs and induces Kupffer cells-mediated pro-fibrotic signaling
-
Apoptotic bodies directly trigger phagocytic activation in HSCs and KCs, worsening fibrosis through multiple routes. To be specific, once HSCs engulf an apoptotic body, it drives assembly of NADPH oxidase subunits into an active NOX2 complex on a phagosome membrane. NADPH consumption by the complex generates superoxide anions, turning on redox pathways and MAPK. Increased expression of COL1A1, COL1A2, and TGFβ1 follows. HSCs activation and extracellular matrix deposition subsequently occur, leading to liver fibrosis[91]. On a separate front, KCs specifically take up apoptotic bodies from dying hepatocytes. Apoptotic body uptake by Kupffer cells stimulates production of Fas ligand, and TNFα promotes neutrophil infiltration and HSCs activation, culminating in more severe liver inflammation and faster fibrosis progression[92]. In a related process, HSCs' engulfment of apoptotic bodies allows extracellular Galectin-3 to crosslink integrin αvβ3, facilitating phagosome binding and internalization. NF-κB signaling then drives higher Galectin-3 expression and secretion from HSCs, which further enhances HSCs' phagocytic activity, HSCs activation, and pro-collagen α1 expression[93]. CCN1 serves as a bridging molecule, binding phosphatidylserine on apoptotic neutrophils and integrin αvβ3 on macrophages simultaneously. Binding triggers macrophage efferocytosis of apoptotic neutrophils. Efferocytosis prompts macrophages to produce TGFβ1, which activates HSCs and drives their differentiation into myofibroblasts[27]. FABP7 upregulates CD36 expression on Kupffer cell surfaces. Increased CD36 expression improves Kupffer cells' phagocytosis of apoptotic cells and encourages Kupffer cell production of MCP1 and TGFβ, which activate HSCs, thereby driving liver fibrosis progression[94] (Fig. 2).
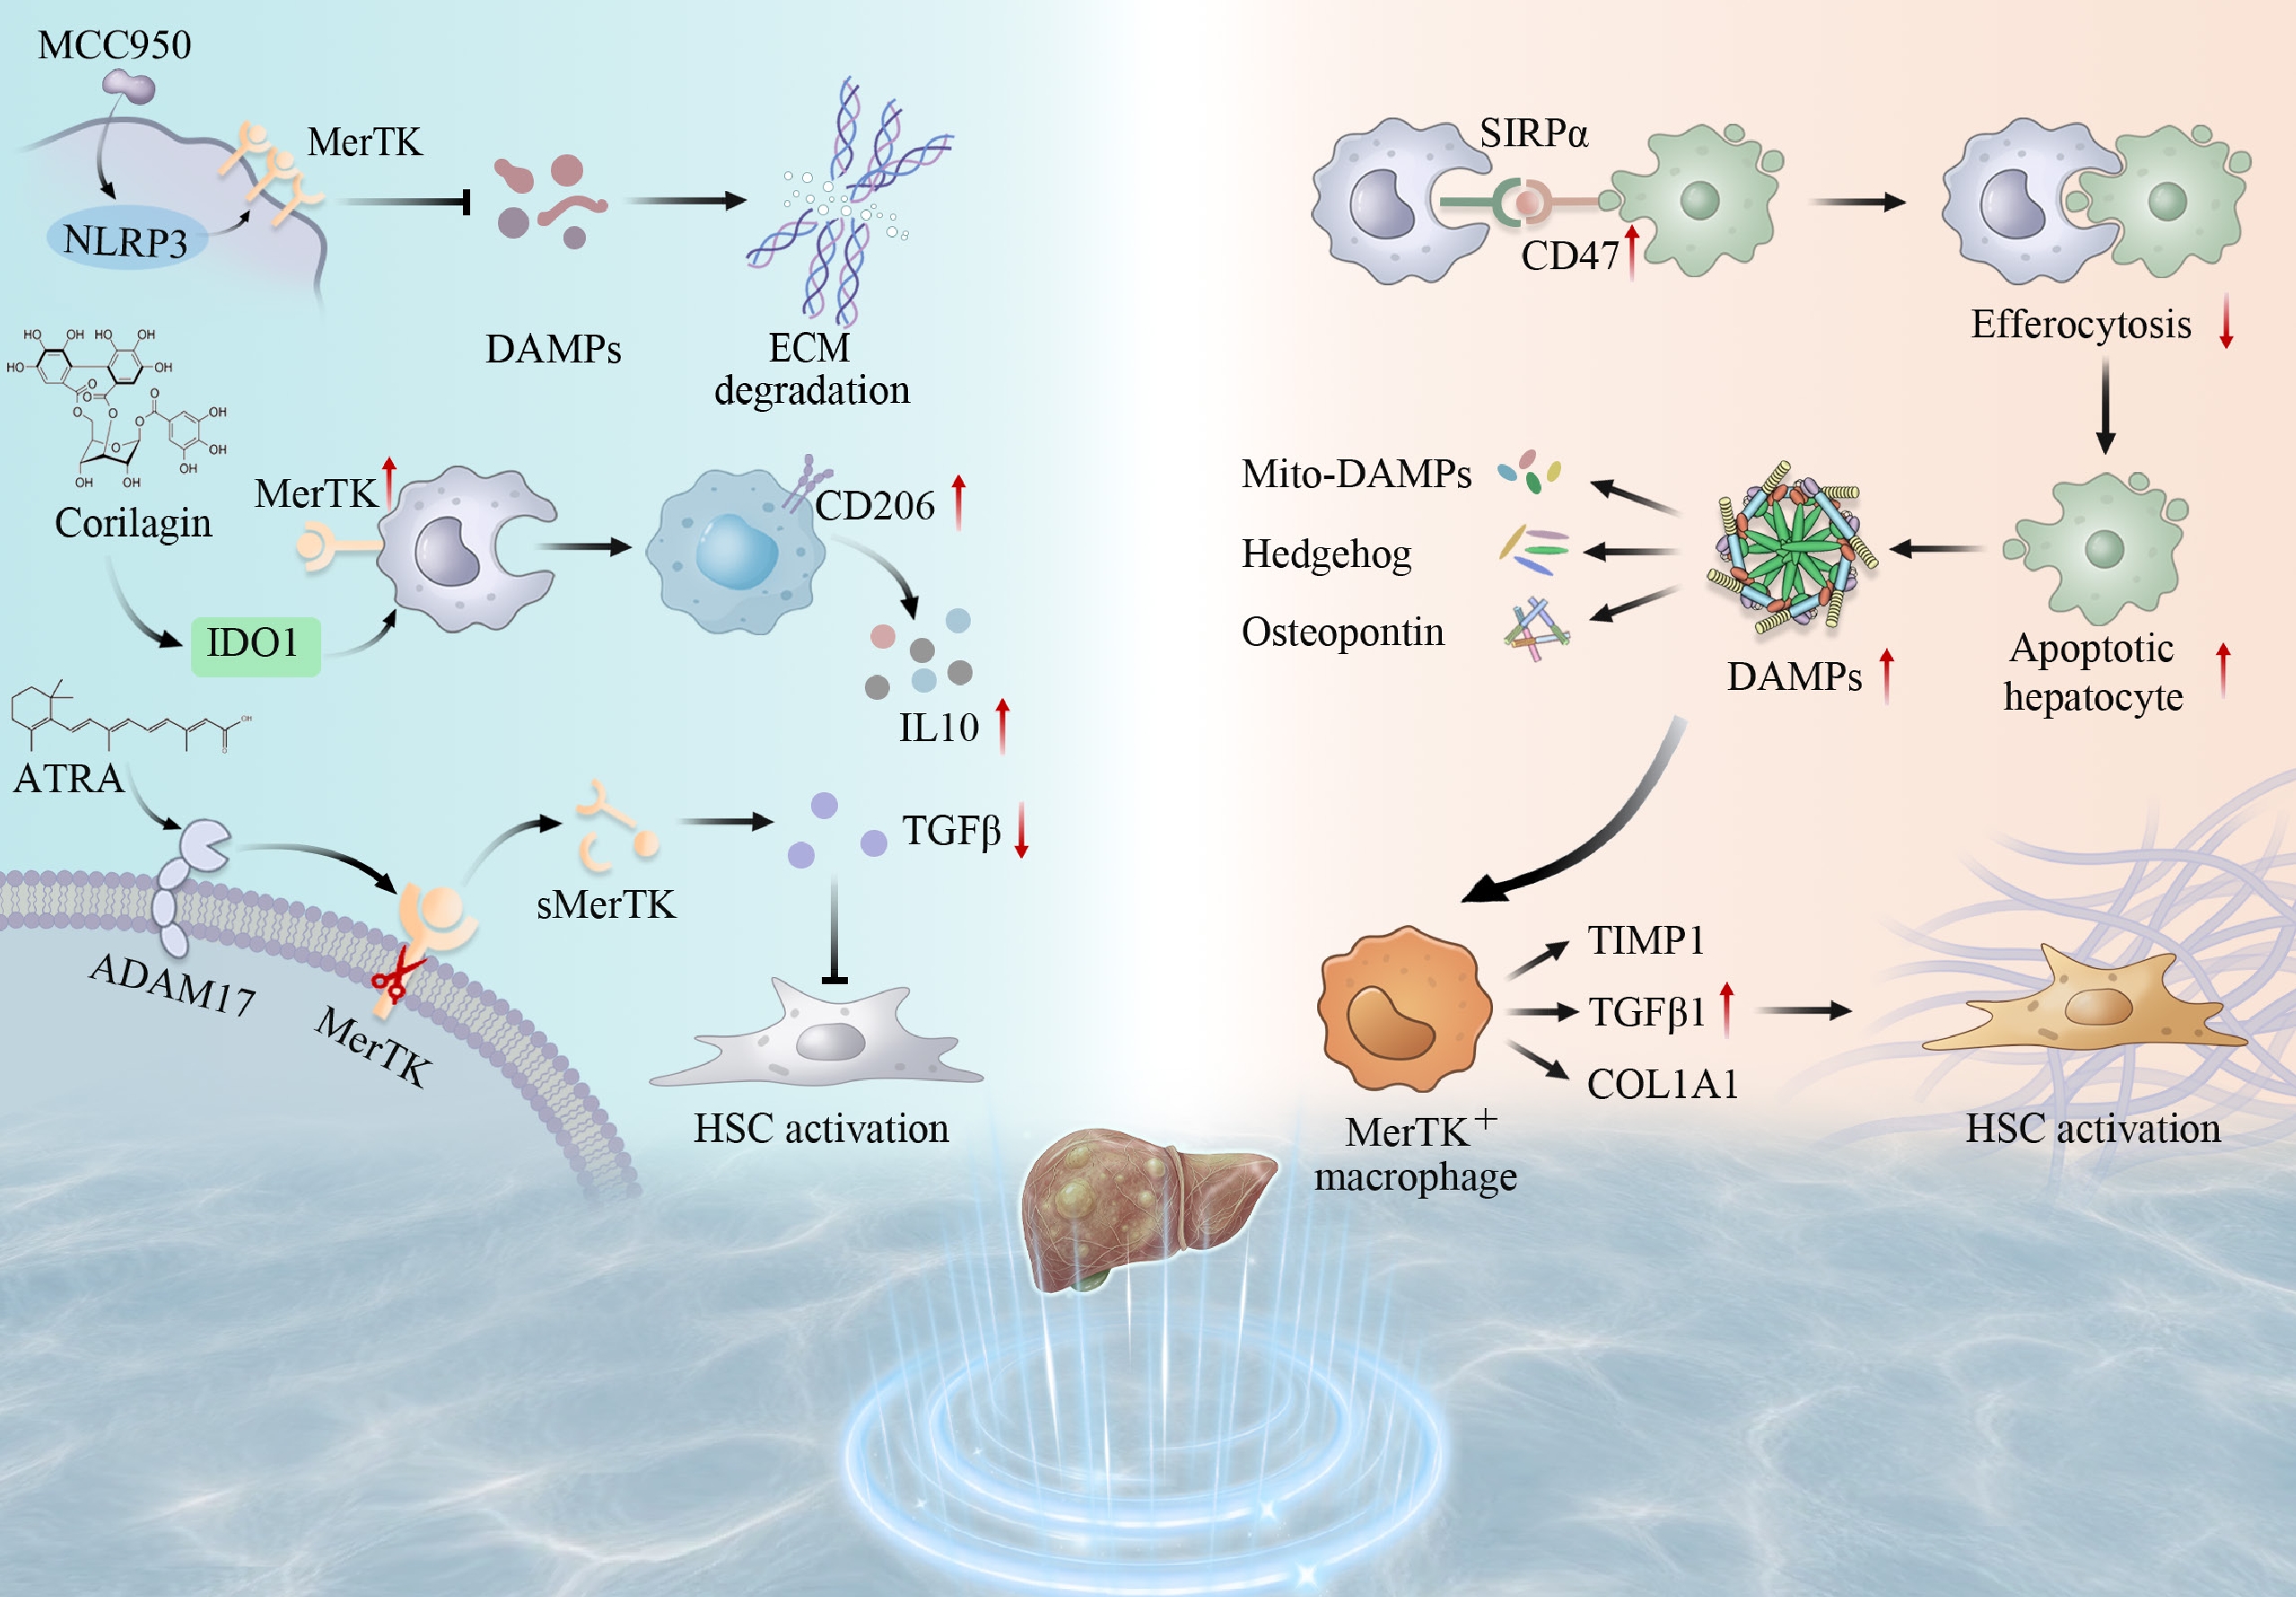
Figure 2.
The dual role of efferocytosis-related molecules in liver fibrosis. In the normal liver, macrophages efficiently clear apoptotic hepatocytes by upregulating MerTK and related molecules, promoting downregulation of TGFβ and TIMP1, thereby exerting anti-fibrotic and pro-resolution effects. In contrast, during liver fibrosis progression, efferocytosis becomes dysfunctional, accompanied by abnormalities in the CD47-SIRPα signaling axis, activation of the NLRP3 inflammasome (which can be inhibited by MCC950), release of DAMPs and mitochondrial DAMPs, ADAM17-mediated shedding of sMerTK, as well as activation of multiple pathways involving Hedgehog, osteopontin, VEGF, IDO1, and IL10. These changes collectively promote HSCs activation and ECM deposition (e.g., COL1A1), ultimately driving fibrosis progression.
In summary, efferocytosis plays two opposing roles in LF. One side supports repair, while the other contributes to damage. Contradictions in published data, TREM2-positive macrophages linked to both protection and disease, or MerTK signaling tied to resolution and progression. This suggest these molecules shift function depending on the liver's pathological state. A fixed label of 'good' or 'bad' does not apply. These observations challenge the traditional M1/M2 classification system. A more useful lens examines macrophage behavior across time and space within injured tissue. Moving forward, efforts may clarify exactly when efferocytosis becomes harmful vs helpful during fibrosis, and intervention strategies should follow suit. Rather than simply turning efferocytosis on or off, future treatments will need to adjust the process stage by stage, guiding the response from broad immune modulation toward precision-based care.
Cell death modalities and efferocytosis outcomes in liver fibrosis
-
Cell death modalities shape the mechanisms and biological outcomes of efferocytosis. Different forms of cell death transmit distinct signals to phagocytes, determining whether phagocytes execute normal anti-inflammatory clearance or trigger aberrant inflammatory responses. ACs clearance represents the primary manifestation of efferocytosis. Apoptotic hepatocytes release S1P, which induces TREM2 expression on macrophages. TREM2-mediated efferocytosis clears lipid-laden apoptotic hepatocytes and reduces production of pro-inflammatory cytokines TNFα and IL1β, thereby alleviating chronic liver inflammation[95]. Pyroptosis involves membrane rupture, release of pro-inflammatory factors (e.g., IL1β), and aberrant 'efferoptosis' with pro-inflammatory outcomes. Although unreported in liver-only fibrosis models, multi-organ fibrosis evidence shows TNF-driven CASPASE8 activation switches homeostatic efferocytosis to lytic pyroptosis, directly maturing IL1β without NLRP3 inflammasome involvement[96]. Necroptosis, also involving membrane rupture, releases abundant pro-inflammatory substances, provoking strong inflammatory responses that impair phagocytic function or cause inflammatory cell death. Effective tissue repair becomes compromised. In NASH, necroptotic hepatocytes upregulate the 'don't-eat-me' ligand CD47, while liver macrophages upregulate the receptor SIRPα. Aberrant activation of the CD47-SIRPα axis impairs macrophage efferocytosis of necroptotic hepatocytes. Persisting uncleared necroptotic hepatocytes release DAMPs, activate HSCs, promote collagen deposition, and ultimately aggravate liver fibrosis[70]. Collectively, the dual role of efferocytosis in liver fibrosis is also modulated by the type of cell death. Whether a given death modality exerts beneficial or detrimental effects requires evaluation in the context of specific disease conditions and downstream signaling pathways.
The dual role of efferocytosis in liver fibrosis: functional divergence of key mediators
-
Key efferocytosis-related molecules play critical roles in liver fibrosis and represent promising therapeutic targets, though the underlying mechanisms remain incompletely understood. Conflicting experimental results for TREM2 and MerTK pose a key question: why do the same molecules exert dual functions? Evidence indicates that the functions depend on multiple contextual factors, including disease status, inflammatory milieu, tissue microenvironment, and immune cell types. The nature of liver injury affects functional outcomes. In acute injury, TREM2 deficiency impairs macrophage phagocytosis, leading to accumulation of apoptotic hepatocytes and release of mitochondrial DAMPs, aggravating inflammation-driven fibrosis[97]. By contrast, in chronic injury, TREM2-positive macrophages exert pro-inflammatory effects through MS4A7-dependent NLRP3 inflammasome activation[98]. Disease stage determines whether the outcome is protective or pathogenic. During active fibrosis progression, TREM2 alleviates fibrosis by suppressing TGFβ/HIF1α-mediated glycolysis and lactate production, thereby reducing histone H4K12 lactylation[99]. During the resolution phase, TREM2 upregulates SPP1 expression and, through osteopontin secretion, remodels the extracellular matrix and promotes inflammation, driving fibrosis progression[86,100]. Macrophage origin and heterogeneity contribute to the divergence. In the steady-state liver, a population of lipid-associated macrophages expressing TREM2, CD9, GPNMB1, and SPP1 localizes near the bile ducts[101]. In chronic liver injury, resident KCs are lost and replaced by monocyte-derived macrophages, with TREM2 expressed in two monocyte-derived subsets. These include those occupying the KCs niche and lipid-associated macrophages[102,103]. Single-cell transcriptomics confirms that TREM2-positive cells originate from either KCs or monocytes, and the two cell types exhibit distinct functions in injury and repair[104]. MerTK, a classical macrophage marker, is broadly expressed on KCs and other liver macrophage populations[103]. In liver fibrosis, MerTK signaling in KCs promotes pro-fibrotic differentiation and drives HSCs activation via TGFβ1 secretion[105].
-
As our understanding of efferocytosis deepens in LF, therapeutic strategies targeting this process are being explored. Receptors and ligands linked to efferocytosis show promise as biomarkers for diagnosing and managing disease. Efferocytosis plays a dual role in LF, acting as both 'friend' and 'enemy'. Given this complexity, therapeutic interventions should be carefully tailored to the specific disease stage and context. This duality gives rise to two therapeutic avenues. One is to enhance protective efferocytosis, which promotes inflammation resolution and tissue repair. The other is to inhibit pathological efferocytosis, which blocks pro-fibrotic signals and HSCs activation. We summarized recent therapeutic strategies targeting cellular sequestration in LF and fibrosis-related liver diseases, e.g., small-molecule compounds, biologics, and nanoparticle delivery systems (Based on
https://clinicaltrials.gov ) (Table 2). We further discuss current translational efforts and implementation barriers. Major challenges include drug resistance, a lack of reliable biomarkers, safety concerns, and limitations in delivery systems (Fig. 3).Table 2. The ongoing clinical trials of associated drugs or therapies in liver fibrosis.
Identifiers Start date Liver fibrosis type Time frame Phase Status NCT04197479 November 2019 NASH with liver fibrosis (stage F2–F3) 52 weeks Phase 3 Active, not recruiting NCT03900429 April 2019 NASH with liver fibrosis (stage F1–F3) 36 weeks Phase 3 Completed NCT04951219 July 2021 NASH with compensated cirrhosis (stage F4) 54 weeks Phase 3 Recruiting − − TIM4 engineered macrophages for MASH-associated
liver fibrosis− Preclinical Preclinical stage − − Anti-CD47 antibody for liver fibrosis − Preclinical Liver fibrosis-specific
trial pending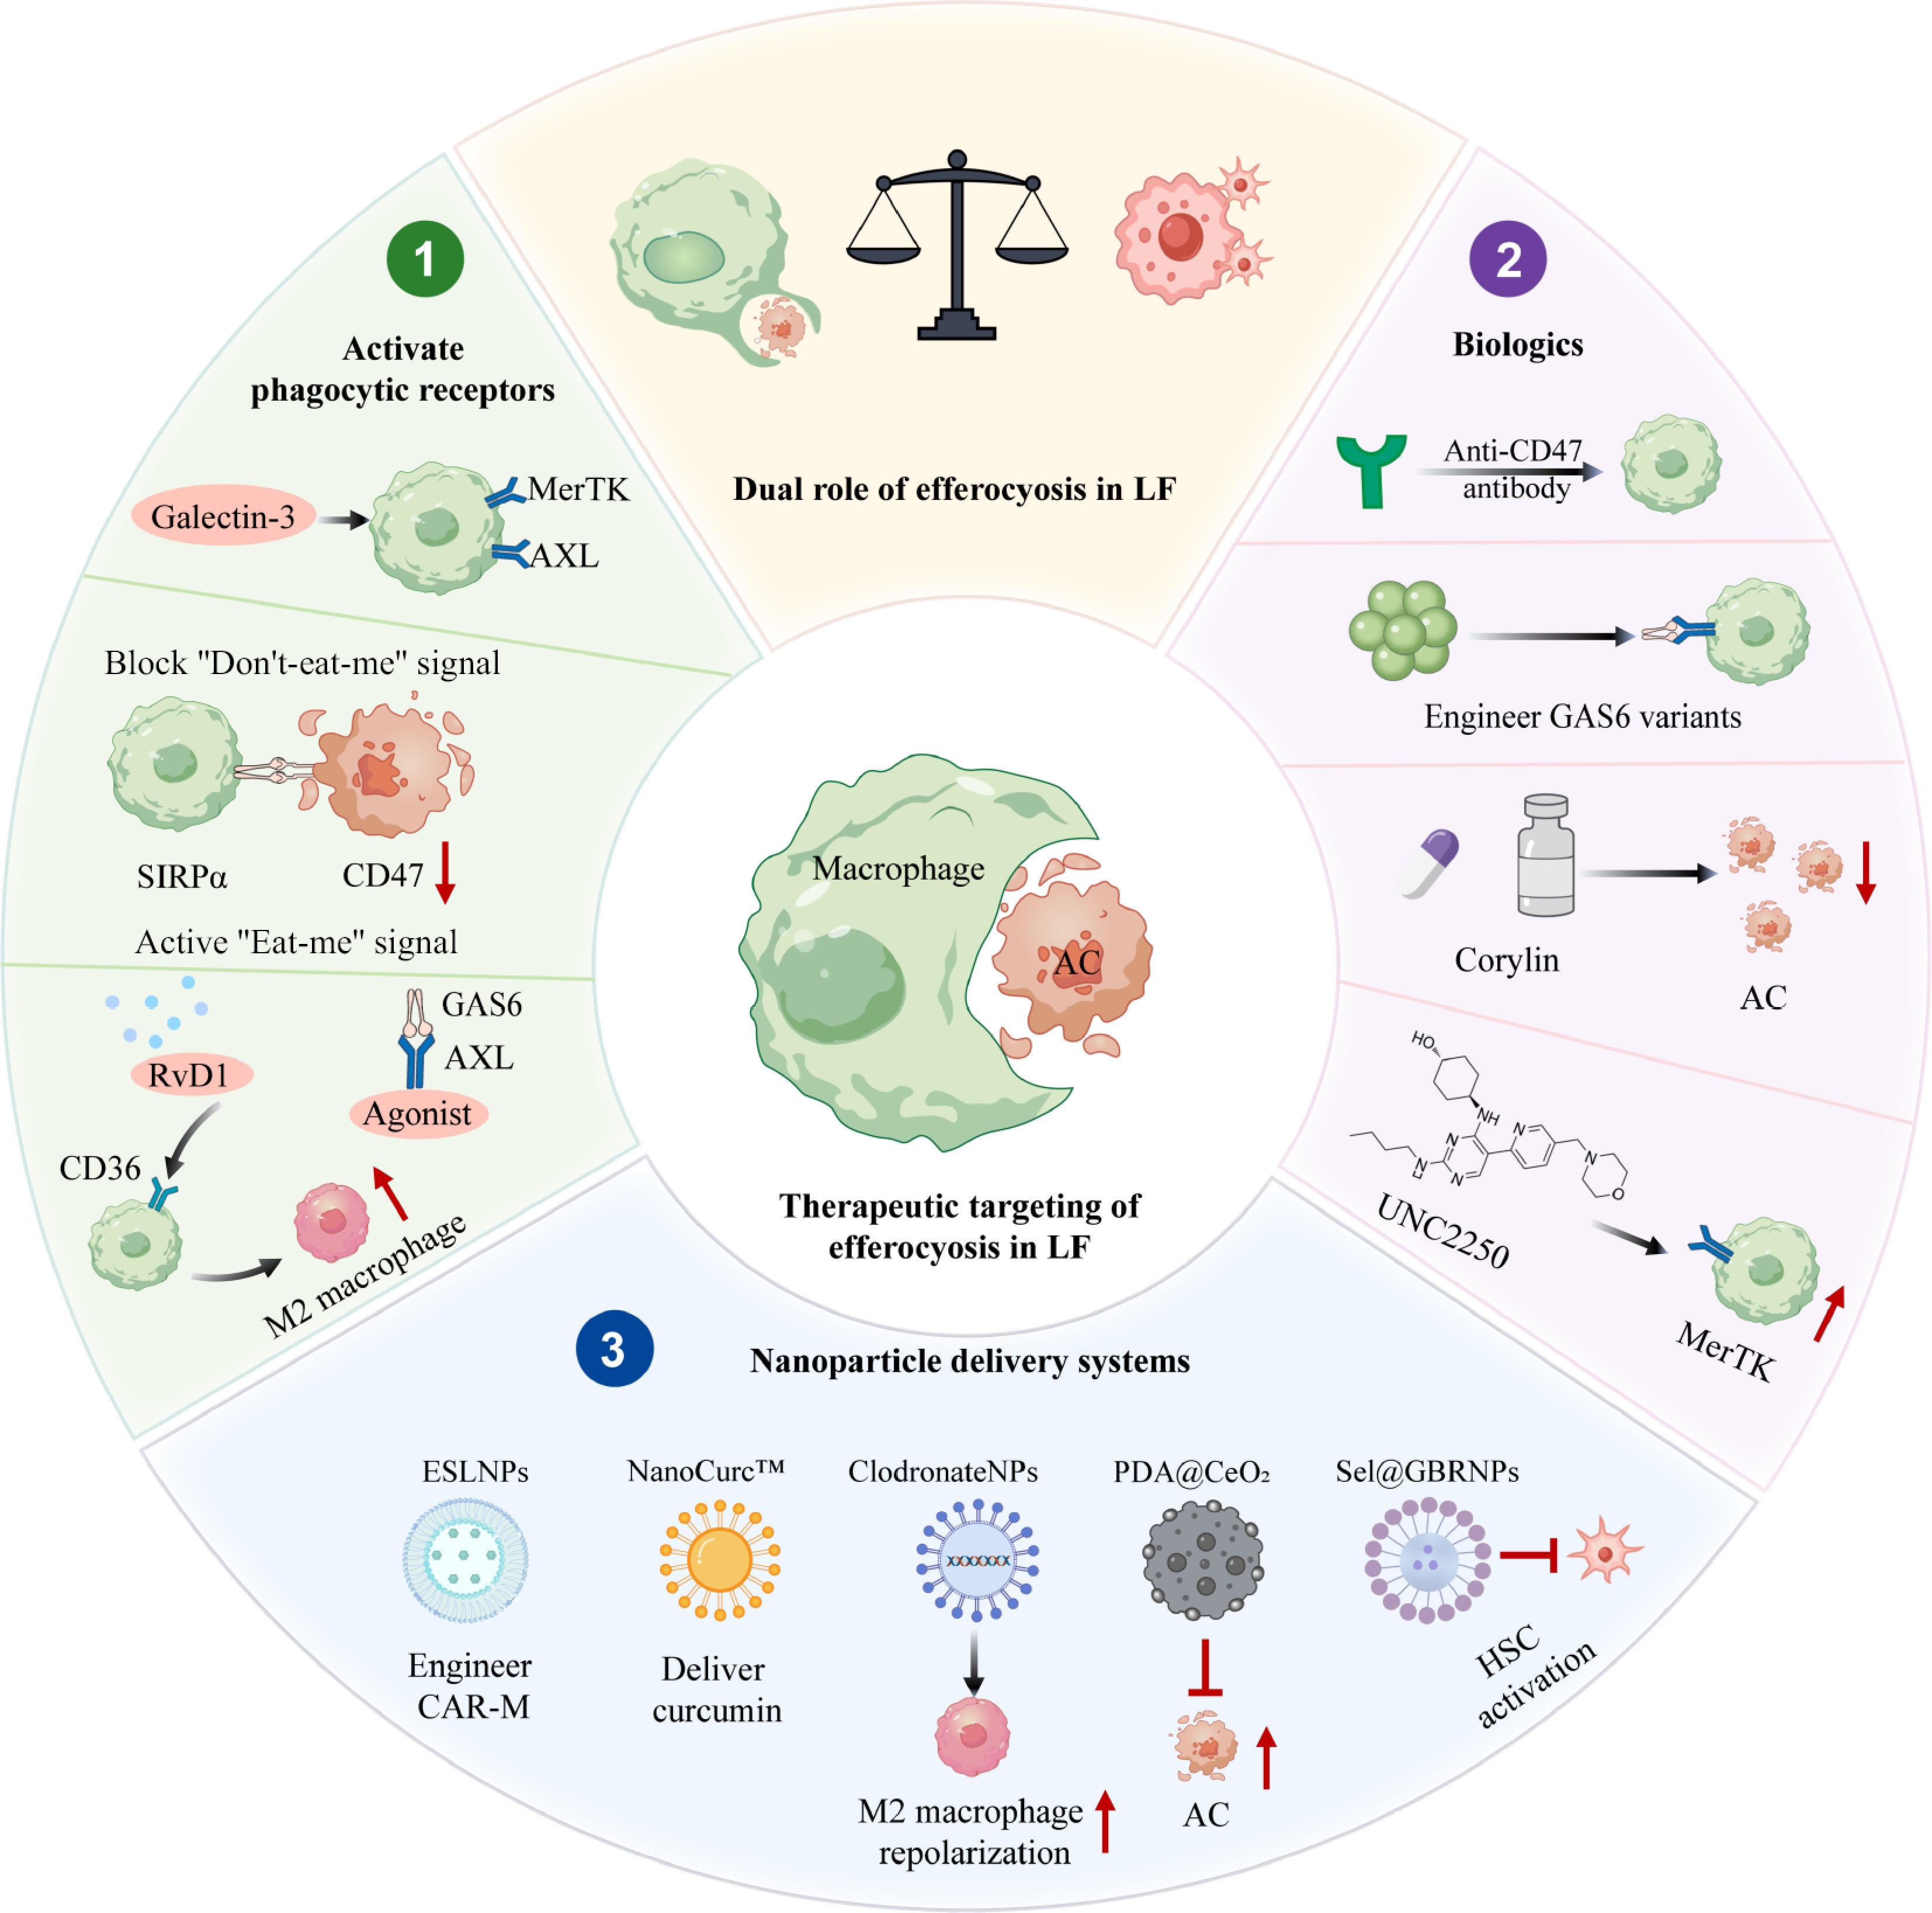
Figure 3.
Therapeutic strategies targeting efferocytosis. This figure outlines efferocytosis-targeted strategies for liver fibrosis, grouped into three main approaches: (1) enhancing protective efferocytosis by blocking CD47-SIRPα, supplementing bridging molecules (e.g., MFGE8), restoring MerTK function, or using engineered GAS6 ligands, (2) inhibiting pathological efferocytosis via AXL/MerTK inhibition, Galectin-3 blockade, or Corylin treatment, and (3) nanoparticle delivery systems including ESLNPs, NanoCurc™, Sel@GBRNPs plus Riociguat, and PDA@CeO2, which enable targeted modulation and promote resolution.
Disrupting 'don't-eat-me' signals targeting phagocytic receptors: strategies to enhance efferocytosis
-
Inadequate clearance of dead hepatocytes by liver macrophages may contribute to LF, indicating that therapies to improve efferocytosis deserve attention. This strategy focuses on removing the molecular 'brakes' that impede efferocytosis. For example, as noted, blocking either CD47 or SIRPa boosts the clearance of necroptotic hepatocytes and dampens the progression to LF[106]. One more tactic is to exploit the tissue-repair properties of pro-resolving mediators, which support resolution and improve efferocytosis. As an illustration, resolvin D1 administration has been found to aid liver repair in experimental models of both ALI and alcohol-associated liver fibrosis[107,108]. Additional pharmacological strategies aimed at enhancing efferocytosis are under investigation. Yet, moving from preclinical promise to bedside reality entails considerable hurdles. Detailed deliberation on the key translational bottlenecks is deferred to 'Open challenges in the clinical translation of efferocytosis' section.
Targeting the efferocytosis receptors remains a promising strategy for treating LF. Across multiple fibrotic disease models, GAS6, AXL, and MerTK emerge as pathological drivers. Based on this connection, several pharmaceutical agents targeting the GAS6, AXL, and MerTK pathways are now advancing in clinical development. On the protective side, positive allosteric modulators of MerTK and AXL ramp up receptor activity and enhance phagocytic clearance, supporting tissue repair[109]. In a CCl4-induced fibrosis model, the AXL inhibitor bemcentinib blocked HSCs activation, reduced collagen deposition, and lowered MMP9 and α-SMA expression[110], administering the TAM ligand GAS6 protected mice from fulminant LF[111]. Blocking GAS6-AXL signaling with a preclinical version of batiraxcept also reduced collagen accumulation in highly desmoplastic tissue[112]. Macrophages carrying MerTK represent a hepatoprotective subset, clearing apoptotic cells to curb post-injury hyperinflammation[113]. Yet the MerTK inhibitor UNC569, a derivative of MRX-2843, suppressed HSCs activation[114]. Galectin-3 appears to push efferocytosis through MerTK, pointing to possible repair pathways[115]. The AMPK agonist A-769662 boosted fatty acid oxidation, restored MerTK expression in macrophages, and eased liver inflammation[116]. Recombinant MFGE8 enhanced efferocytosis, maintained chondrocyte function, delayed aging markers, and shifted macrophages toward an anti-inflammatory profile[117]. Recent years have brought major advances in understanding efferocytosis receptor biology in LF. These insights have fueled development of both family-wide inhibitors and receptor-specific blockers targeting AXL or MerTK[118]. What remains unclear is exactly which combinations or solitary inhibitors will translate into clinical success.
Biologics in efferocytosis-targeted therapy
-
Biologics offer another key strategy for improving efferocytosis. Current approaches focus on three areas: targeting membrane proteins, engineering natural ligands, or modifying metabolic pathways after efferocytosis. One example is an anti-CD147 antibody. This therapy enhances phagocytosis in LF and has passed phase I safety trials[119]. Other researchers engineer tissue-targeted TGFβ proteins. These molecules accumulate specifically at damaged sites and stimulate MerTK expression, resulting in longer-lasting effects than unmodified TGFβ[120]. Engineered GAS6 variants with high receptor affinity also promote phagocytosis while limiting inflammation[121]. In human HSCs assays, cabozantinib blocks GAS6-induced AKT activation. Since GAS6 binds the AXL receptor, this inhibition reduces stellate cell proliferation and fibrogenic activity[122]. Separate work shows corylin triggers CASP9 and CASP3, pushing stellate cells toward apoptosis[111]. Certain structurally optimized mediators achieve broader effects by activating the MerTK-ARG1 pathway while suppressing glycolysis, reprogramming inflammatory responses[123]. PEP2-8 restores MerTK-dependent efferocytosis in endothelial cells, reducing both cellular senescence and systemic inflammation[124]. Collectively, these successful cases highlight the clinical promise of targeting efferocytosis.
Advanced drug delivery strategies for efferocytosis enhancement
-
Nanomedicines designed to engage efferocytosis-related receptors, highly expressed on phagocyte surfaces, offer a promising therapeutic strategy in preclinical liver disease models. Efferocytosis-sparked lipid nanoparticles (ESLNPs) enable the engineering of fibrosis-associated macrophages into anti-inflammatory CAR-Ms through co-delivery of TRIM13 mRNA and mRNA encoding an anti-fibroblast activation protein (FAP) CAR[125]. NanoCurc™ facilitates delivery of curcumin, an anti-apoptotic compound, effectively mitigating the CCl4-induced liver fibrosis model[126]. Additional strategies include anti-miR-155 for M1 to M2 macrophage repolarization and clodronate-loaded nanocomplexes that modulate macrophage activity by mimicking efferocytosis effects[127]. The PDA@CeO2 system, integrating short-fiber sponges with apoptotic cell-mimicking CeO2 nanozymes, promotes sustained macrophage efferocytosis to accelerate inflammation resolution and tissue repair[128]. A synergistic approach combining riociguat with hepatocyte-targeted bilirubin nanomedicine (Sel@GBRNPs) reduces ROS and apoptosis, attenuating HSCs activation and extracellular matrix deposition[129]. While the specificity and targeting merits of nanomedicine-based efferocytosis strategies have been recognized, significant barriers still obstruct translation to clinical use. A detailed breakdown of the key impediments is reserved for 'Open challenges in the clinical translation of efferocytosis' section.
Open challenges in the clinical translation of efferocytosis
-
Despite the promising preclinical evidence supporting efferocytosis-targeting strategies, their clinical translation for early-stage liver fibrosis and cirrhosis remains at an exploratory stage. Numerous unresolved obstacles prevent full translation of the approaches. One major concern is acquired resistance over time, driven by compensatory upregulation of alternative phagocytic checkpoints or elevated CD47 expression. Candidate biomarkers (sMerTK, sTREM2, GAS6) lack adequate validation. Circulating levels fluctuate with liver injury and inflammation. Tissue origins and correlations with local efferocytosis remain unclear. Consequently, target engagement and early response cannot be reliably gauged. Nanomedicine delivery introduces additional barriers. Nanomedicine platforms suffer from batch-to-batch variability, low synthetic yields, rapid reticuloendothelial clearance, and poor penetration through dense fibrotic ECM. Pathological conditions may alter ligand binding to MerTK or TREM2, while receptor presence in healthy tissues raises off-target safety concerns. Future efforts should focus on simplified manufacturing, improved ligand targeting, and thorough safety assessments.
-
This review takes a close look at how efferocytosis plays a key role in LF and explores how biologics and nanomedicine enhance these biological processes. Efferocytosis consists of four core phases recruitment, recognition, internalization, and digestion-that operate as a continuous dynamic process. ACs send out ATP and CX3CL1 signals to lure phagocytes. Phosphatidylserine exposure, influenced by 'eat-me' and 'don't-eat-me' signals, governs recognition. Internalization requires RAC1-driven changes in the cytoskeleton, and digestion involves RAB GTPases and LC3-associated phagocytosis for degrading cargo. We dig into the basics of how efferocytosis works at the molecular level and its physiological impact on liver fibrosis to better understand the two-sided role in the disease. First off, most studies suggest that when liver macrophages clear out dead hepatocyte cells, it actually helps protect against LF. But on the flip side, some research shows that in certain lab models, including those triggered by CCl4 or BDL, the same process drives fibrosis instead[130]. This isn't too shocking, since tissue repair leaves scars, and efferocytosis tends to ramp up TGFβ, a key player in liver scarring[131]. Plus, when HSCs clear dead cells, it may trigger their activation and kickstart LF; further validation is required to elucidate the significance of this mechanism[93]. Given all this, lots of factors shape how efferocytosis behaves in LF, so the precise molecular mechanisms remain largely unclear. The biggest challenge is that efferocytosis is constantly changing. In chronic stages, how well efferocytosis works, which cells are involved, and the molecular pathways at play vary a lot depending on time and location. Another hurdle is the lack of reliable tools to track efferocytosis in real time as the process unfolds.
Considering these obstacles, we suggest several novel viewpoints: (1) from static images to dynamic spatiotemporal analysis: current methods offer endpoint measurements with limited spatial and temporal resolution. Three complementary tools: intravital imaging for real-time phagocytosis capture, lineage tracing for tracking macrophage dynamics across fibrotic stages, and MRI/PET for non-invasive organ-level fibrosis assessment together generate a spatiotemporal efferocytosis atlas from cellular to whole-organ scales; (2) from single-cell to spatial transcriptomics: tissue sections receive dual labeling for apoptotic cells and phagocyte subtypes. Spatial transcriptomic profiling is performed at multiple fibrotic time points. Together, these approaches permit in situ assessment of distribution and clearance, thereby indicating whether efferocytosis defects concentrate within scarred areas; (3) from traditional characterization to AI-supported analysis: live imaging, spatial transcriptomics, and MRI/PET data are fed into AI models. The models detect critical phases when efferocytosis changes from protection to pathology, e.g., macrophage phenotype shifts. Detected phases support intervention timing based on disease stage. In conclusion, this review provides researchers with a thorough understanding of the essential role of efferocytosis in LF. We aspire for this review to inspire more scholars to engage in this area and jointly advance treatment development.
-
Not applicable.
-
The authors confirm contributions to the work as follows: study conception, manuscript revision and supervision: Chen X, Sun Y, Wang H; Draft manuscript preparation, figure creation: Chen Y, Chen X; critical revision and expert input: Liu Y, Wang H. All authors reviewed and approved the final version of the manuscript.
-
Data sharing is not applicable to this review as no datasets were generated or analyzed.
-
The authors declare that there is no conflict of interest.
- Copyright: © 2026 by the author(s). Published by Maximum Academic Press on behalf of China Pharmaceutical University. This article is an open access article distributed under Creative Commons Attribution License (CC BY 4.0), visit https://creativecommons.org/licenses/by/4.0/.
-
About this article
Cite this article
Chen Y, Sun Y, Chen X, Liu Y, Wang H. 2026. Drugging the efferocytosis process for treating hepatic fibrosis: dual roles, mechanisms, and therapeutics. Targetome 2(4): e032 doi: 10.48130/targetome-0026-0031 
Drugging the efferocytosis process for treating hepatic fibrosis: dual roles, mechanisms, and therapeutics
- Received: 24 May 2026
- Revised: 30 June 2026
- Accepted: 02 July 2026
- Published online: 22 July 2026
Abstract: The removal of apoptotic cells by phagocytes, called 'efferocytosis', is vital for preserving tissue homeostasis. Faulty efferocytosis contributes to a rising list of chronic inflammatory diseases, including liver fibrosis (LF). A major characteristic of LF is ongoing, unresolved inflammation, usually linked to an overactive immune response, oxidative stress, imbalances between proteases and antiproteases, and heightened cell death. This process activates hepatic stellate cells, resulting in an overaccumulation of extracellular matrix. Although excessive cell death in LF is well documented, new findings emphasize issues in the following clearance process, called efferocytosis. Thus far, studies have indicated that upon LF, liver-resident Kupffer cells and macrophages from infiltrating monocytes are involved in clearing apoptotic cells, limiting inflammation, and repairing damage. Efferocytosis facilitates LF in rare situations, including the prolonged release of transforming growth factor-beta during continuous injury repair and the accumulation of uncleared ACs that emit damage-associated molecular patterns, which may result in sustained activation. This process leads to ongoing inflammation and ECM buildup. Our knowledge of how liver macrophages execute efferocytosis and malfunctions in LF is still incomplete. In this review, we critically analyse the study and highlight the significant duality of efferocytosis in the pathogenesis of LF. Herein, we suggest future paths for fundamental and clinical research in LF, emphasizing new treatment possibilities that focus on the root causes of the disease instead of just alleviating symptoms.
-
Key words:
- Liver fibrosis /
- Efferocytosis /
- Liver macrophages /
- HSCs /
- Therapeutic strategies