










-
Pancreatic ductal adenocarcinoma (PDAC) is one of the most lethal malignancies, with a 5-year relative survival rate of merely 13%, and is estimated to become the second leading cause of cancer death by 2030[1,2]. Surgical resection and chemotherapy serve as the main options for PDAC patients[3]. However, up to 80% of PDAC patients are diagnosed at advanced stages and precluded from surgery, while adverse responses and rapid development of resistance to chemotherapy have been broadly reported[4−7]. Moreover, the efficacy of many targeted therapies in PDAC clinical trials is limited, and the application of immunotherapy remains controversial and requires further investigation and validation[2]. Therefore, there is an urgent need to identify vulnerabilities and develop novel therapeutic strategies and interventions against PDAC.
PDAC carcinogenesis results from molecular alterations in cancer cells and cellular alterations to the non-cancerous tumor microenvironment (TME)[8]. Dvorak suggested in the 1980s that tumor stroma was the result of wound healing gone awry, which modulated the vascular supply, metabolite exchange, and immune cell infiltration to support cancer progression and metastasis; thus, targeting tumor stroma might serve as a potential approach to cancer interventions[9,10]. However, it has been reported that single inhibition of components in the TME has demonstrated subtle and even negative responses in PDAC experimental and clinical studies[11,12], indicating the importance of comprehensively investigating and understanding the pro-tumorigenic and anti-tumorigenic properties and interactions of different components of the TME in PDAC.
The application of Chinese herbal medicine (CHM) in cancer treatment has been explored over the past several decades and has been shown to possess anti-tumor properties and few side effects[13]. In accordance with its philosophy of holism and retaining balance, CHM has been verified to play a therapeutic role in a multi-component, multi-target, and multi-stage way[13]. Recent studies investigating the effects of CHM on TME have also revealed its role in modulating immune cells by maintaining Th1/Th2 balance, regulating macrophage polarization, and suppressing angiogenesis[14]. This review aims to summarize CHM formulae, herbs, and active compounds derived from natural medical materials that modulate single or multiple TME components in PDAC and their underlying mechanisms.
-
As mentioned above, the TME is one of the major factors shaping and interacting with pancreatic cancer cells (PCCs) that create a favorable environment for tumorigenesis, progression, and metastasis, while it also significantly contributes to the development of therapeutic resistance[15].
Compositions
-
The TME is a complex ecosystem with heterogeneity and dynamics, composed of cancer cells, stromal cells, extracellular matrix (ECM), infiltrating immune cells, vasculature, nerves, microbiome, and a large number of signaling molecules[15], as shown in Fig. 1.
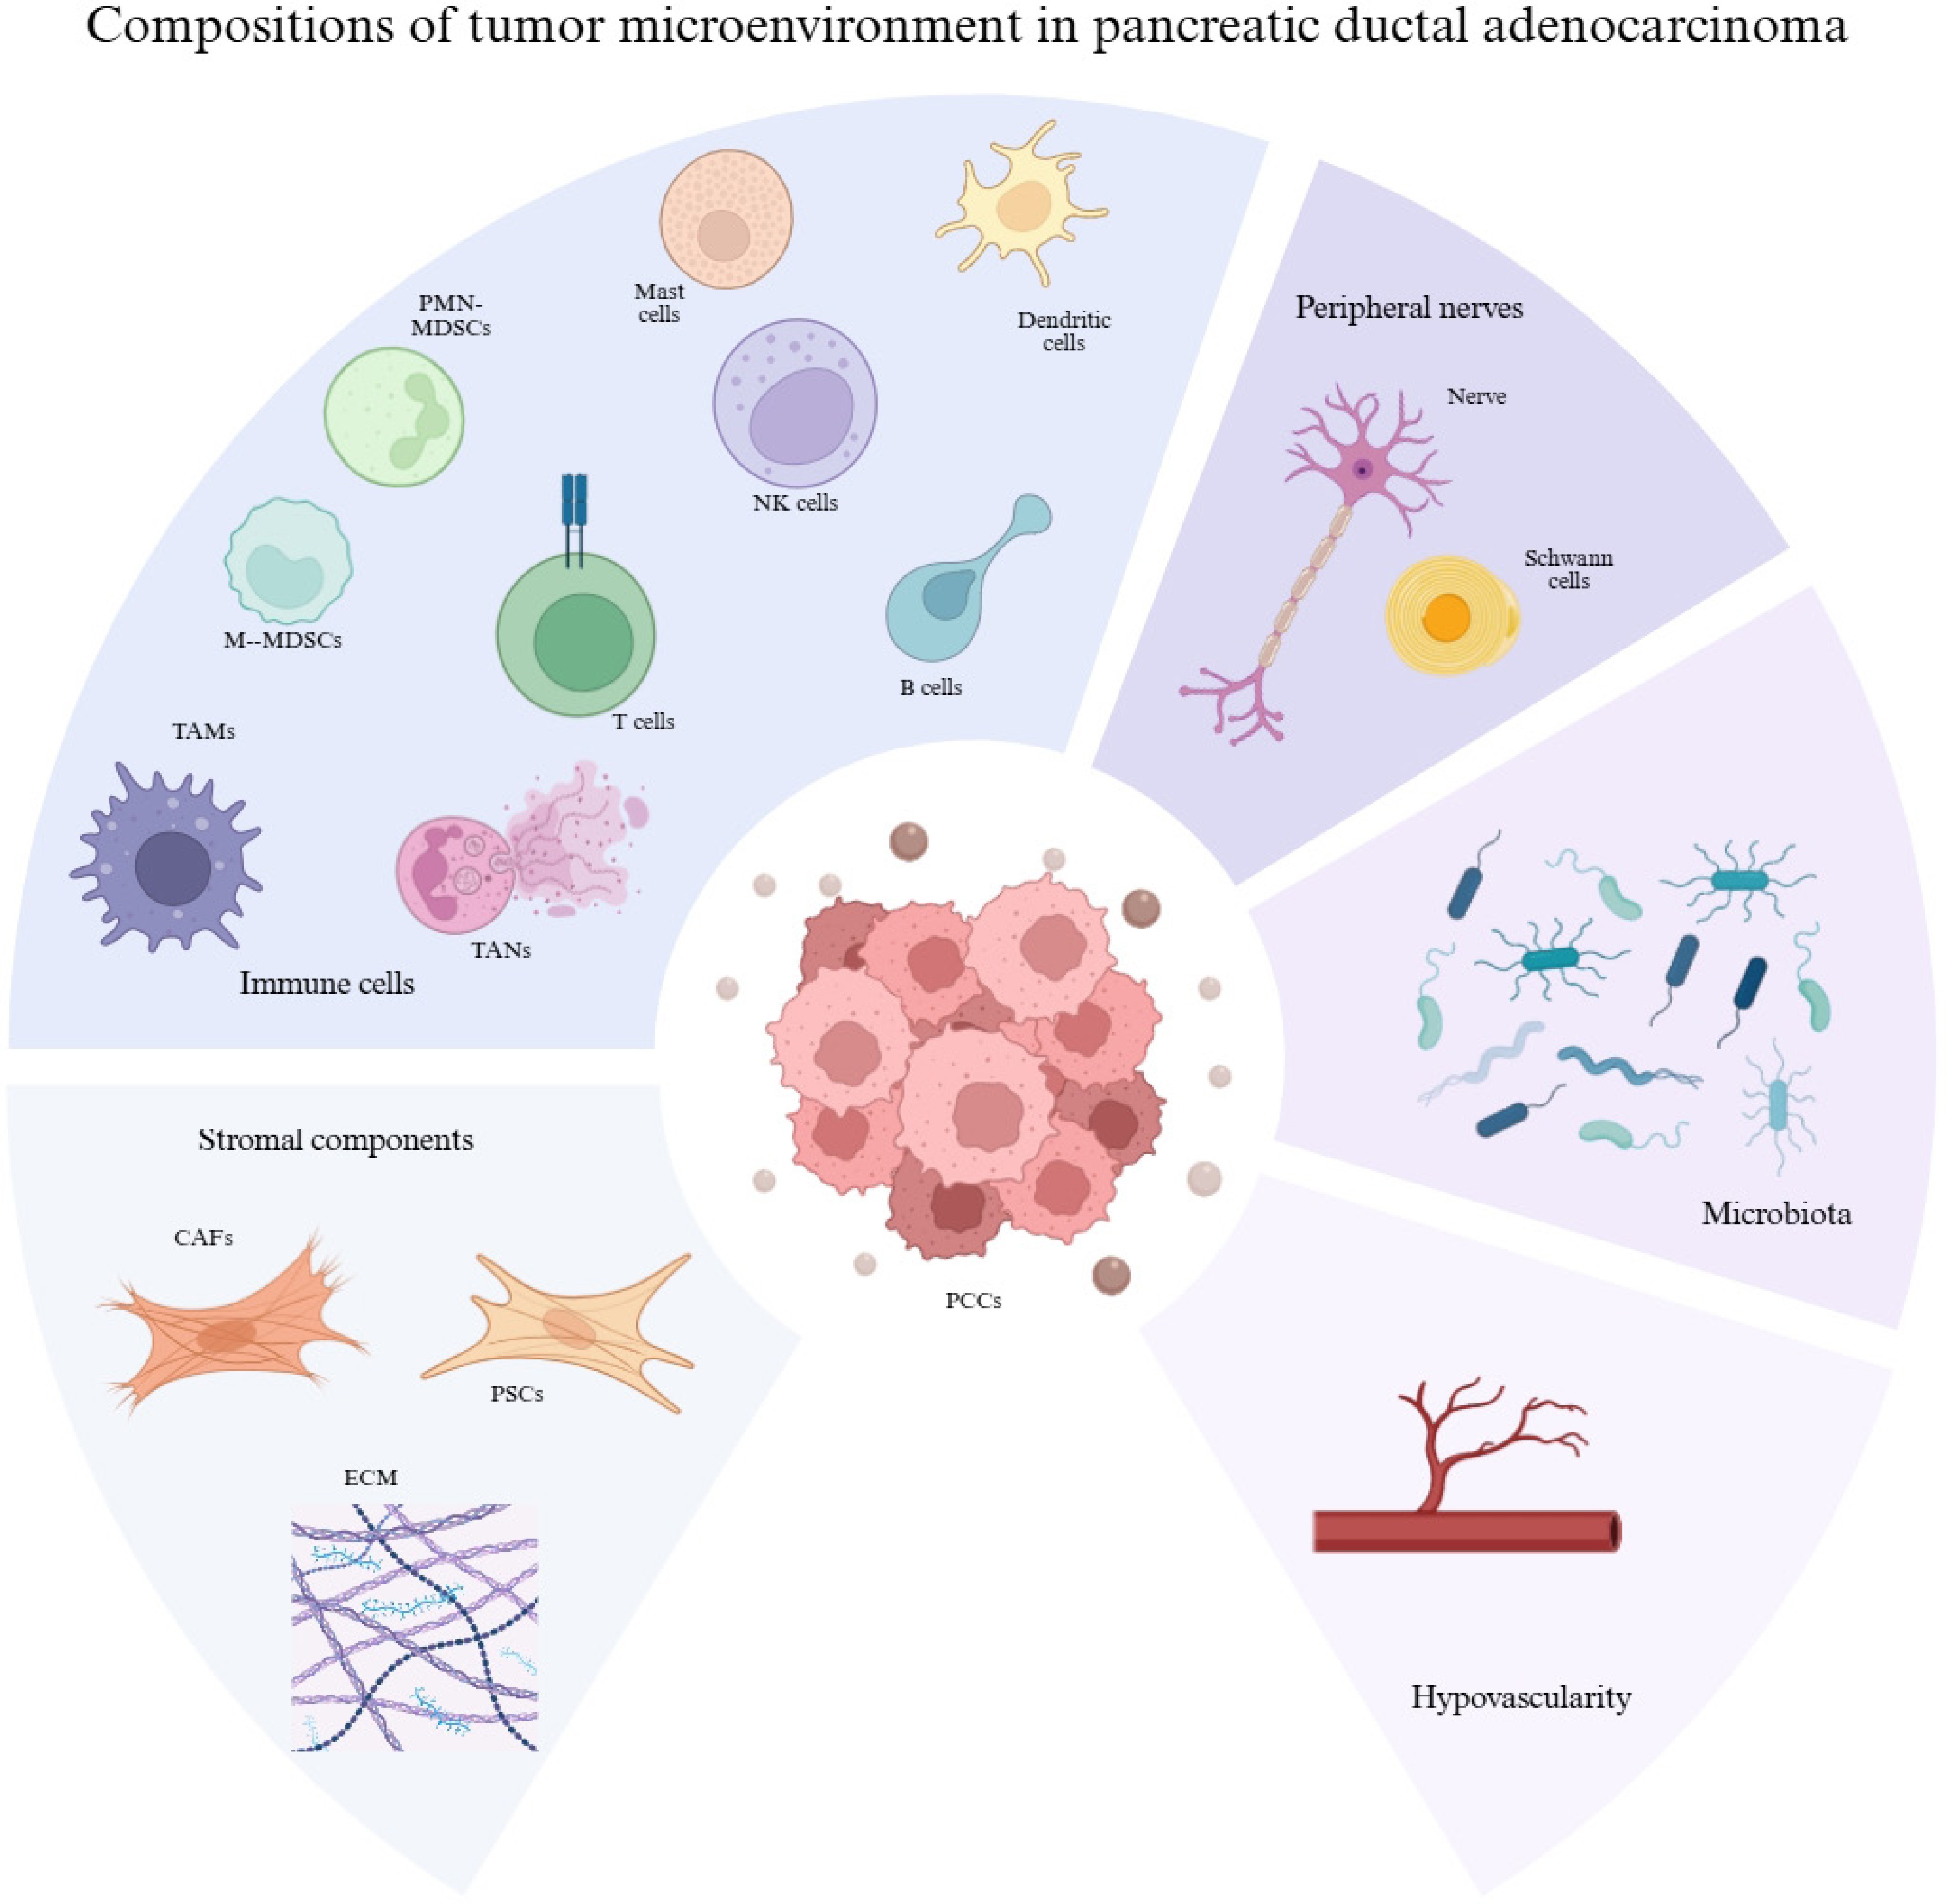
Figure 1.
Components of the TME in PDAC. Heterogenous CAFs and PSCs produce materials for ECM formation and contribute to desmoplasia. The immune cells infiltrated into tumors include TAMs, TANs, MDSCs, Treg cells, cytotoxic T cells, B cells, NK cells, and so on, creating an immunosuppressive environment. Microbiota, neurons, and vasculature also serve as important constituents of the TME in PDAC.
Stromal components
-
Stromal cells primarily include pancreatic stellate cells (PSCs) and cancer-associated fibroblasts (CAFs). PSCs are activated during the pathogenesis of PDAC with excessive expression of alpha-smooth muscle actin (α-SMA) and abnormal ECM production, and are composed of myofibroblast, smooth muscle cell (SMC)-like, and inflammatory subclusters[16,17]. The fibroblastic phenotype serves as a main precursor for CAFs, which can also be differentiated from various other cellular sources, exert functional heterogeneity, and possess the potential for interconversion, including myofibroblastic (myCAFs), inflammatory CAFs (iCAFs), and antigen-presenting CAFs (apCAFs)[18,19]. CAFs primarily produce components for the ECM, such as the most abundant proteins, fibrillar collagens, proteoglycans, and hyaluronan, which contribute to water retention, high pressure, and impaired vascular perfusion in the TME[20,21]. The rigid matrix of ECM physically inhibits the infiltration of immune cells, while some of the matrix-modifying enzymes conversely promote the recruitment of immunosuppressive cells such as TAMs, creating a cancer-promoting immunological 'cold' TME for PDAC growth[22]. Furthermore, ECM collagens have been revealed to be closely correlated with the overall survival of PDAC patients, either positively or negatively, determined by their cellular origin and structural differences and thus differentiation of anti-tumorigenic and pro-tumorigenic functions[23,24].
Immune cells
-
Infiltrating immune cells are mainly composed of tumor-associated macrophages (TAMs), tumor-associated neutrophils (TANs), myeloid-derived suppressor cells (MDSCs), T cells, B cells, natural killer (NK) cells, and so on. TAMs play an essential role in immunosuppression and carcinogenesis, closely correlated with clinical outcomes[25−27]. TAM subpopulations differ in tumor-restrictive (M1) and tumor-promoting (M2) phenotypes as well, which can be influenced by tissue-specific factors induced by environmental stimuli[22]. For example, embryonically derived TAMs promote fibrosis by activating CAF secretion and directly induce ECM deposition or remodeling, while monocyte-derived TAMs have been observed to be involved in higher levels of antigen presentation and immunomodulation[27,28].
Traditionally, TANs are classified into anti-tumor N1 and pro-tumor N2 phenotypes[24]. N1 can induce direct cytotoxicity via DNA damage, mutations, and antigen-dependent trogocytosis, secreting tumor necrosis factor (TNF) and enhancing pro-inflammatory response[29,30]. Conversely, neutrophil extracellular traps (NETs), constructed from NETosis, can suppress the activity of NK cells and cytotoxic T cells by physically forming a protective network and modulating arginase-1 (ARG1) and cytokine secretion[30−34]. Moreover, it has been hypothesized that the cluster of TANs and circulating tumor cells (CTCs) presents a more efficient metastasis pattern with enhanced cell cycle progression[35].
MDSCs can induce T-cell inhibition by producing reactive oxygen species and nitric oxide and expressing high levels of ARG1[36,37]. The two main subpopulations, polymorphonuclear MDSCs (PMN-MDSCs) and mononuclear MDSCs (M-MDSCs), both possess the function of suppressing T cells, and the latter is suggested to be more restrictive[38−40]. Therefore, targeting the entire myeloid cell subsets might be an alternative strategy[37].
Immune exhaustion, especially in CD8+ T cells, is present in PDAC and is characterized by loss of effector function and inhibitory receptors such as PD-1, while FOXP3+CD4+CD25+ T cells (Tregs) are recruited into tumors and induce effector T cell lysis, cytokine release, and immune checkpoint expression[41,42]. An increased Treg/CD8+ T cell ratio is correlated with the inferior outcome of PDAC[43]. However, downregulation or loss of FOXP3 expression has been reported to induce helper T (Th) cell-like activated immune response and pro-inflammatory cytokine secretion such as IFNγ[44,45]. Impaired cytotoxic function of NK cells is detected in PDAC patients, whose progression of cancer is associated with CD96 and CD226 derived from NK cells[46,47]. Other components such as PSCs and TAMs also participate in inhibiting NK cell cytotoxicity[48].
Vasculature
-
Compressed massively by the dense stroma, the vasculature in the PDAC TME is significantly distinct from other malignancies, with a low microvessel density (MVD) and leaky structure, resulting in high interstitial fluid pressure, decreased blood perfusion and thus hypoxia, an acidic TME, retarded drug delivery, and immunosuppression[49−51]. However, the nutrient needs of PCCs in an active metabolic state can still be fulfilled by basal microvilli, a unique microvasculature facilitating high glucose uptake with glucose transport-1-positive vesicles[52].
Peripheral nerves
-
Neural components in the TME have attracted growing research interest recently. Perineural invasion (PNI), a hallmark of PDAC, contributes to local progression and intraneural spread of PCCs[53,54]. Activated Schwann cells have been shown to promote cancer cells via midkine signaling, enhance the differentiation of CAFs to a pro-tumor phenotype by IL-1α secretion, and increase accumulation of MDSCs, resulting in tumor progression and immunosuppression[55]. Acetylcholine released from cholinergic signaling is observed to inhibit production of IFN-γ by CD8+ T cells and decrease the Th1/Th2 ratio[56]. Moreover, serine secreted by axonal extensions of neurons helps nourish cancer cells in the deserted TME[57].
Microbiota
-
The role of microbiota in PDAC is being explored continuously. For instance, increased bacterial and fungal DNA load has been identified in PDAC tumors, and the signatures of microbiota, where specific microbial species manifest enriched abundance, are also suggested to be associated with clinical outcomes[58−60]. Emerging evidence has been provided for the anti-tumor effects induced by ablation of microbes in animal models, while specific species and their metabolites, such as short-chain fatty acids, indole derivatives, bile acids, polyamines, and purines, have distinct pro-tumor and anti-tumor functions directly on cancer cells or via immunomodulation, pointing out the necessity of further mechanistic and functional studies involving diverse cohorts of PDAC subjects[61,62].
Several studies have found that compensatory effects exist in the single depletion of a certain component of the TME. For example, single depletion of MDSCs induces an increase in macrophages and monocytes[63]. Additionally, depletion of TREM2+TAMs has been suggested to trigger pathogenic inflammation and accelerate tumor deterioration[64,65]. These findings, together with the plasticity and heterogeneity of TME components, indicate the need to develop a highly selective and multifaceted targeted strategy, with the aim of tilting the functional state of these components towards a tumor-suppressive or baseline state.
Role of the TME in PDAC metastasis
-
The TME participates in the PDAC metastatic cascade through direct action on PCCs as well as indirect modulation of signaling molecules and formation of a permissive environment, resulting in dissemination of cancer cells into the bloodstream, lymphatic vasculature, and perineural invasion (PNI)[15,66]. Firstly, hypoxia, a consequence of hypovascularity resulting from desmoplasia created by CAFs and ECM, is essential for the metastatic potential of PCCs[67]. Meanwhile, epithelial-to-mesenchymal transition (EMT) is required for the initiation of cancer cell migration, which is induced by the signal molecules derived from the TME, such as TAM-derived TGF-β[15,67]. In secondary sites, prometastatic niche formation is regulated by microenvironmental factors released from the primary site[68]. For example, CAFs in the primary TME have been found to secrete IL-6, which upregulates STAT3 signaling and activates hepatocytes, promoting the prometastatic niche and thus liver metastasis[69].
Role of the TME in PDAC therapeutic resistance
-
Fibrosis and hypovascularity are two significant characteristics of the PDAC TME. The densely fibrotic stroma works as a physical barrier and possibly traps proangiogenic factors, resulting in decreased vascularity[70]. Vascular perfusion is correlated with cellular infiltration, drug penetration and distribution, and the TME effectively suppresses the efficacy of immunotherapy and chemotoxicity via selective anti-tumor leukocyte exclusion and hindered drug delivery, respectively[15,71]. PSCs have also been shown to limit the effect of gemcitabine by entrapping it in the cytoplasm[72]. With prominent heterogeneity and plasticity, the TME in PDAC demonstrates resilience and pliability, enabling the tumor to withstand various therapies and develop acquired resistance. For example, ATP released from cancer cell death into the TME in response to cytotoxic agents is converted to immunosuppressive adenosine that recruits myeloid cells and inflammatory cells[73,74]. Moreover, resistance also develops in therapies targeting adoptive responses, such as antagonizing CCR2 to limit monocyte recruitment, which leads to increased TAN infiltration[75]. These findings underscore the importance of a multifaceted strategy in reversing therapeutic resistance and improving efficacy.
Effects and mechanisms of CHM in targeting TME components
-
As mentioned above, a multipronged strategy might outweigh single depletion, where TCM can exploit its advantage of retaining holistic balance. A total of seven herbal formulae involving 44 herbs, one herbal extract, and 14 active compounds were identified with therapeutic effects by targeting the TME in PDAC. These CHM formulae, herbs, and compounds mainly modulate the TME by targeting CAFs, TAMs, TANs, PSCs, MDSCs, cytotoxic T cells, Tregs, NK cells, and vasculature.
Targeting PSCs
-
Phoenix dactylifera L. is considered to contain abundant nutrients, while research also found that its extracts could modulate the TME by reducing the activity and fibrotic phenotype of PSCs and thus ameliorating fibrosis, a mechanism involving suppressed fibronectin 1 (FN1) and α-SMA expression[76]. Resveratrol (RSV) possessed the properties of targeting PSCs as well. The dysregulation of HIF-1α and SDF-1 induced by hypoxia was observed to be reversed by RSV in cancer cells, and PSC-derived α-SMA, IL-6, and SDF-1 were suppressed[77]. Moreover, RSV could inhibit ROS-induced miR-21 and glycolysis in PSCs, with an increase in PTEN expression[78]. Specifically, trans-resveratrol (TRSV) demonstrated an effect of inhibiting viability and fibrotic mediators of PSCs by downregulating Acta2, Col2-α1, α-SMA, and FN1 expression, with NF-κB and AKT signaling suppressed[79].
Targeting CAFs
-
The Qing-Yi-Hua-Ji (QYHJ) formula, composed of Scutellariae Barbatae Herba, Hedyoti Diffusae Herba, Amorphopallus Ribieri Rhizoma, Coicis Semen, Gynostemmatis Pentaphylli Herba, Ganoderma, and Amomi Rotundus Fructus, is a representative of CHM designed for PDAC in clinical practice. It is suggested to suppress the proliferative activity of CAFs with decreased SDF-1, α-SMA, and vimentin[80]. α-mangostin (α-M), which is extracted from pericarps of mangosteen widely used in folk medicine, was suggested to have TME-modulatory properties. A study utilizing a nanoplatform to enhance the biodistribution of α-M found that the nanoparticles decreased FN, α-SMA, and FAP-α expression and viability of NIH3T3 cells, as well as facilitated vascular normalization and thus increased blood perfusion, mainly through blocking the TGF-β/Smad pathway and inhibiting phosphorylated Smad2/3[81]. Curcumin from Curcuma longa was shown to directly inhibit the proliferation and mesenchymal characteristics of CAFs, which were observed from increased E-cadherin, decreased Vimentin, and α-SMA[82]. A study employing a CAF-tailored nanosystem that loaded quercetin (QUE) was found to inhibit α-SMA and Wnt16 in NIH3T3 cells, leading to remodeling of the TME where FN and collagen were remarkably reduced, P-gp induced by high levels of HIF-1α was reversed, and thus amelioration of drug resistance[83].
Targeting ECM
-
Huachansu (HCS), isolated from dried skin glands of Bufonis Venenum, manifested ECM suppressive effects via decreasing collagen type-1, TGF-β1, and Smad2/3 expression of the TGF-β/Smad pathway in PSCs[84].
Targeting vasculature
-
The Dahuang Zhechong Pill (DHZCP) is a classical formula that resolves blood stasis and was found to significantly reduce tumor size and NF-κB and VEGF expression, combined with TNS4 knockdown[85]. Danggui-Sayuk-Ga-Osuyu-Saenggang-Tang (DSGOST), which is Danggui-Sini-Jia-Wuzhuyu-Shengjian-Tang in Chinese, was found to inhibit VEGF-dependent angiogenesis by directly blocking the binding of VEGF to VEGFR2, restricting VEGF-dependent phosphorylation of VEGFR2, FAK, SRC, AKT, IKKα/β, IκBα, and NF-κB in human umbilical vein endothelial cells (HUVECs), and inhibiting NF-κB-dependent MM9 expression[86]. Sauchinone, a bioactive compound of Saururus chinensis, was found capable of inhibiting VEGF and HIF-1α expression, as well as the Wnt/β-catenin signaling pathway[87]. Sophorae Flavescentis Radix is commonly used in diseases of the digestive system, whose compound oxymatrine was revealed to downregulate angiogenesis by suppressing NF-κB-mediated VEGF signaling[88]. Ursolic acid (UA) was observed to reduce a series of proteins related to angiogenic function, including VEGF, VEGFR2, and CD31, with decreased STAT3 phosphorylation[89]. Emodin, an anthraquinone that can be isolated from diverse TCM herbs, manifested an effect of inhibiting angiogenesis by modulating TGFβ/Smad signaling and miRNA, including a decrease in miR-155, miR-210, TGF-βI, IL-6, and Angptl4 expression and an increase in miR-20b, TβRI, TβRII, and Smad4[90].
Targeting TAMs
-
The QYHJ formula, apart from inhibiting CAFs, exerts suppressive effects on TAM infiltration as well, with a decrease in IL-6 and CCL5[80,91]. Xihuang Pill (XHP), consisting of Calculus Bovis, Moschus, Olibanum, and Myrrha, demonstrates TAM modulation. It could promote the polarization of macrophages towards an M1 phenotype by increasing CXCL9 and CXCL10 expression that are closely associated with anti-tumor immune cell recruitment, as well as inhibiting the Kyn-Ahr axis in RAW264.7 cells, with an increase in CD86 and a decrease in CD206[92]. Modified Sijunzi Decoction (MSJZD), which is composed of Rhizoma Poria, Codonopsis Radix, Rhodiolae Crenulatae Radix et Rhizoma, Atractylodis Macrocephalae Rhizoma, Glycyrrhizae Radix et Rhizoma, and Dioscoreae Rhizoma, was identified with effects on tumor suppression and immune modulation. The infiltration of TAMs was switched to M1 phenotype dominance, and thus the secretion of ARG1, IL-10, IL-6, and PPARγ by M2 macrophages was inhibited[93]. Osthole extracted from Cnidii Fructus exerted the functions of targeting TAMs by inhibiting both M2 macrophage infiltration and polarization via suppressing STAT6 and C/EBP β signaling pathways, with MRC1, CCL22, and TGF-β expression decreased, as well as blocking phosphorylation of STAT6 and ERK1/2[94]. Icarrin, one of the active compounds of Epimedii Herba, is suggested to decrease infiltration and the number of M2 macrophages, which is achieved by downregulating the STAT6 signaling pathway in RAW 264.7 cells[95]. Isobavachalcone (IBC), one of the active compounds of Psoraleae Fructus, mediates attenuation of M2 macrophages[96]. Bupleuri Radix is one of the most used herbs in clinical practice, whose active compound Saikosaponin D (SSD) exerts immunomodulatory effects on the TME. By downregulating the STAT6 and PI3K/AKT/mTOR signaling pathways, polarization of macrophages towards M2 phenotypes is inhibited in both RAW 264.7 and primary bone marrow cells, while infiltration of M2-TAMs into tumors is also blocked[97].
Targeting TANs
-
A study investigating the effects of Pi Ji Pill (PJP) demonstrated that it can modulate the immune TME, where the expression of CD45, F4/80, and Ly6G/Ly6c was upregulated, and IL-8 was downregulated[98]. Specifically, PJP was also suggested to inhibit NET production with downregulation of neutrophil elastase (NE), MPO, and CitH3[98].
Targeting MDSCs
-
Icarrin, apart from decreasing M2-TAMs in both the TME and spleen, is also able to restrain infiltration of PMN-MDSCs in tumor and spleen populations[95]. After treatment of IBC, the infiltration of MDSCs is also inhibited, with an attenuated expression of ARG1 and TGF-β[96]. Following the suppressive M2 polarization induced by SSD, PMN-MDSCs were also restrained in both the tumor and spleen[97].
Targeting T cells
-
Juzen-Taihoto (TJ-48), which is Shi-Quan-Da-Bu decoction in CHM, was investigated in clinical trials involving PDAC patients of advanced stage. After administration, CD4/CD8 ratios increased, while a significant decrease in the Treg population was observed, with no major side effects reported, indicating the modulation of the immune response towards an anti-tumor state by TJ-48[99]. MSJZD was also associated with increased CD8+ T cell infiltration with elevated L-arginine levels, as a result of reduced ARG1 secretion by M2-TAMs[93]. After treatment of IBC, elevated accumulation of CD8+ T cells was also detected[96]. Regulated by the polarization of TAMs, CD3+, CD8+, and T cell infiltration in tumors was enhanced in the SSD treatment group as well[97].
Targeting NK cells
-
The cytotoxicity and CD27 expression of NK cells were reported to be downregulated by M2-TAMs. Researchers also found that SSD can restore NK cell activity at the primary tumor site with inhibition of M2-polarization[97].
In conclusion, CHM modulates the TME in PDAC in a multi-target, multi-pathway manner, with mechanisms that include suppressing the fibrotic activity of PSCs and CAFs, remodeling the ECM, regulating the polarization of TAMs, inhibiting MDSC recruitment, NET production, and angiogenesis, as well as inducing cytotoxic T cell and NK cell infiltration. Multiple signaling pathways are involved, such as C/EBP β, NF-κB, TGFβ/Smad, PI3K/AKT, JAK1/STAT3, and STAT6. These CHMs are classified based on the components they target, and the underlying mechanisms are summarized in Table 1 and Fig. 2.
Table 1. TME-modulatory effects and corresponding mechanisms of CHM formulae, herbs and active compounds.
Target CHM formula/extract/compound Constituents/solvent/origins Model Effect TME-modulatory mechanisms Ref. PSCs Phoenix Dactylifera L. Water, EtOH, acetone, EtOAc extracts PSCs ↓ PSCs’ fibrotic phenotype ↓ FN1, α-SMA
↑ antioxidant capacity[76] Resveratrol Multiple PSCs
PANC-1 cells↓ PSCs activation, migration, invasion
↓ ROS-induced glycolysis in PSCs↓ α-SMA
↓ ROS/miR-21
↑ PTEN[78] PSCs
PANC-1, Mia Paca-2 cells
KPC mice↓ PSCs activation ↓ HIF-1α, α-SMA, SDF-1, IL-6 [77] Trans-resveratol Multiple LTC-14 cells ↓ PSCs
↓ Fibrotic mediators↓ α-SMA, FN1
↓ Acta2, Fn1, Col2-α1
↓ p-AKT
↓ NF-κB and AKT signaling[79] CAFs Qing-Yi-Hua-Ji formula Scutellariae Barbatae Herba, Hedyoti Diffusae Herba, Amorphopallus Ribieri Rhizoma, Coicis Semen, Gynostemmatis Pentaphylli Herba, Ganoderma, Amomi Rotundus Fructus Panc02 cells
C57 mice↓ CAFs proliferative activity ↓ SDF-1, α-SMA, vimentin [80] α-Mangostin Mangosteen NIH3T3
PANC-1, PANC-1-Luc2 cells
BALB/c nude mice↓ CAFs
↑ Vascular normalization↓ α-SMA, FAP-α, FN
↓ TGF-β, p-Smad2, p-Smad3
↓ TGF-β/Smad signaling[91] Curcumin Curcumae Longae Rhizoma CAFs
Capan-1, PANC-1 cells,
BALB/c nude mice↓ CAFs
↓ Mesenchymal characteristic↓ Vimentin, α-SMA [82] Quercetin Multiple NIH3T3 cells
Panc02, Panc02-luc cells
C57BL/6 mice↓ CAFs
↑ Blood perfusion↓ α-SMA, Wnt 16
↓ HIF-1α, FN, collagen[83] ECM Huachansu Bufonis Venenum PSCs
SW1990 cells
BALB/c-nu mice↓ ECM ↓ collagen-1
↑ Smad4
↓ Smad2/3, p-Smad2/3
↓ TGF-β/Smad2/3 pathway[84] Vasculature Dahuang Zhechong pill Rhei Radix et Rhizoma, Eupolyphaga seu Steleophaga, Armeniacae Amarum Semen, Persicae Semen, Scutellariae Radix, Rehmanniae Radix, Paeoniae Alba Radix, Glycyrrhizae Radix, Tabanus, Hirudo, Holotrichia Sauteri Moser, Toxicodendri Resina CFPAC-1 cells
Nude mice↓ Angiogenesis ↓ VEGF, NF-κB [85] Danggui-Sayuk-Ga-Osuyu-Saenggang-Tang Radix Angelicae Sinensis, Cinnamomi Cortex, Paeoniae Alba Radix, Clematidis Armandii Caulis, Asari Radix et Rhizoma, Glycyrrhizae Radix, Jujubae Fructus, Evodiae Fructus, Zingiberis Rhizoma Recens HUVECs
Panc-28-luc cells
BALB/c nude mice↓ HUVECs/HDMECs migration, invasion, and tube formation
↓ Vascular leakage↓ Phosphorylation of VEGFR2, FAK, SRC, AKT, IKKα/β, IκBα, NF-κB
↓ MMP-9
↓ VEGF binding to VEGFR2[86] Sauchinone Saururi Herba PANC-1, BxPC-3 cells ↓ Tumor blood flow ↓ VEGF, HIF-1α [87] Oxymatrine Sophorae Flavescentis Radix PANC-1 cells
BALB/C (nu/nu) mice↓ Angiogenesis ↓ NF-κB-mediated VEGF [88] Ursolic acid Multiple AsPC-1, MIA PaCa-2, Panc-28 cells
Athymic nu/nu mice↓ Angiogenesis ↓ VEGF, VEGFR2, CD31
↓ p-STAT3
↓ STAT3 signaling[89] Emodin Multiple SW1990 cells
BALB/c nu/nu mice↓ Angiogenesis ↑ TβRI, TβRII, Smad4
↓ TGF-βI, Angptl4
↑ miR-20b
↓ miR-155 and miR-210[90] TAMs Qingyihuaji formula Scutellariae Barbatae Herba, Hedyoti Diffusae Herba, Amorphopallus Ribieri Rhizoma, Coicis Semen, Gynostemmatis Pentaphylli Herba, Ganoderma, Amomi Rotundus Fructus BxPC, SW1990 cells
BALB/c-nu/nu nude mice↓ TAMs ↓ IL-6 [91] Panc02 cells
C57 mice↓ TAMs ↓ CCL5 [80] Xihuang pill Bovis Calculus, Moschus, Olibanum, Myrrha RAW 264.7 cells Panc02, Panc02-luc cells
C57BL/6J mice↑ M1-TAMs
↓ M2-TAMs↑ CXCL9, CXCL10, Cd86
↓ Cd206
↓ Kyn-AhR axis
↓ AKT/mTOR pathway[92] Modified Sijunzi decoction Poria, Codonopsis Radix, Rhodiolae Crenulatae Radix et Rhizoma Atractylodis, Atractylodis Macrocephalae Rhizoma, Glycyrrhizae Radix et Rhizoma, Dioscoreae Rhizoma Panc02 cells
C57BL/6 mice↑ M1-TAMs
↓ M2-TAMs↓ ARG1, IL-10, IL-6, PPARγ [93] Osthole Cnidii Fructus RAW 264.7
Panc02 cells
C57BL/6 mice↓ M2-TAMs infiltration ↓M2 polarization ↓ MRC1, CCL22, TGF-β
↓ p-ERK1/2, p-STAT6
↓ STAT6 and C/EBP β signaling:[94] Icarrin Epimedii Herba RAW 264.7
Panc02 cells
C57BL/6 mice↓ M2-TAMs infiltration
↓ M2 polarization↓ ARG1, MRC1
↓ p-STAT6
↓ STAT6 signaling[95] Isobavachalcone Fructus Psoraleae RAW 264.7
Panc02 cells
C57BL/6 mice↓ M2-TAMs infiltration
↓ M2 polarization↓ ARG1, MRC1 [96] Saikosaponin D Bupleuri Radix RAW 264.7, H7, BMDM
Panc02 cells
C57BL/6 mice↑ M1-TAMs
↓ M2-TAMs↓ STAT6 and PI3K/AKT/mTOR in RAW264.7 cells [97] TANs Piji pills Curcuma Rhizoma, Sparganii Rhizoma, Alpiniae Officinarum Rhizoma, Pericarpium Citri Reticulatae Viride, Aucklandiae Radix, Gleditsiae Abnormalis Fructus, Pulvis Fumi Carbonisatus HL-60 cells
SW1990
BALB/c nude mice↓ NETs ↑ CD45, F4/80, Ly6G/Ly6C, IL-8
↓ NE, MPO, CitH3[98] MDSCs Icarrin Epimedii Herba RAW 264.7 cells
Panc02 cells
C57BL/6 mice↓ PMN-MDSCs [95] Isobavachalcone Fructus Psoraleae RAW 264.7 cells
Panc02 cells
C57BL/6 mice↓ MDSCs ↓ ARG, TGFβ [96] Saikosaponin D Bupleuri Radix H7, RAW 264.7, BMDM cells
Panc02 cells
C57BL/6 mice↓ PMN-MDSCs [97] T cells Juzen-Taiboto Codonopsis Radix, Atractylodis Rhizoma Alba, Rhizoma Poria, Glycyrrhizae Radix et Rhizoma, Rehmanniae Radix Preparata, Paeoniae Radix Alba, Chuanxiong Rhizoma, Angelicae Sinensis Radix, Astragali Radix, and Cinnamomi Cortex Clinical trial ↑ CD4/CD8 cells
↓ Treg cells[99] Modified Sijunzi decoction Poria, Codonopsis Radix, Rhodiolae Crenulatae Radix et Rhizoma Atractylodis, Atractylodis Macrocephalae Rhizoma, Glycyrrhizae Radix et Rhizoma, Dioscoreae Rhizoma Panc02 cells
C57BL/6 mice↑ CD8+ T cells ↑ L-arginine [93] Isobavachalcone Fructus Psoraleae RAW 264.7 cells
Panc02 cells
C57BL/6 mice↑ CD8+T cells [96] Saikosaponin D Bupleuri Radix H7, RAW 264.7, BMDM cells
Panc02 cells
C57BL/6 mice↑ CD3+CD8+ cells [97] NK cells Juzen-Taiboto Codonopsis Radix, Atractylodis Rhizoma Alba, Rhizoma Poria, Glycyrrhizae Radix et Rhizoma, Rehmanniae Radix Preparata, Paeoniae Radix Alba, Chuanxiong Rhizoma, Angelicae Sinensis Radix, Astragali Radix, and Cinnamomi Cortex Clinical trial ↑ NK cells [99] Saikosaponin D Bupleuri Radix H7, RAW 264.7, BMDM cells
Panc02 cells
C57BL/6 mice↑ NK cells [97] ARG1: Arginase-1; BMDM: Bone marrow mononuclear cells; CAFs: Cancer-associated fibroblasts; ECM: Extracellular matrix; FN: Fibronectin; Glut1: Glucose transporter 1; HDMECs: Human dermal microvascular endothelial cells; HIF: Hypoxia-Inducible Factors; HUVECs: Human umbilical vein endothelial cells; IL: Interleukin; MDSCs: Myeloid-derived suppressor cells; NETs: Neutrophil extracellular traps; NK: Natural killer; PMN-MDSCs: Polymorphonuclear myeloid-derived suppressor cells; PSCs: Pancreatic stellate cells; ROS: Reactive oxygen species; TAMs: Tumor-associated macrophages; TANs:Tumor-associated neutrophils; TGF-β: Transforming growth factor-β; Treg: Regulatory T. α-SMA: Alpha-smooth muscle actin; ↓: Decreased level; ↑: Elevated level. 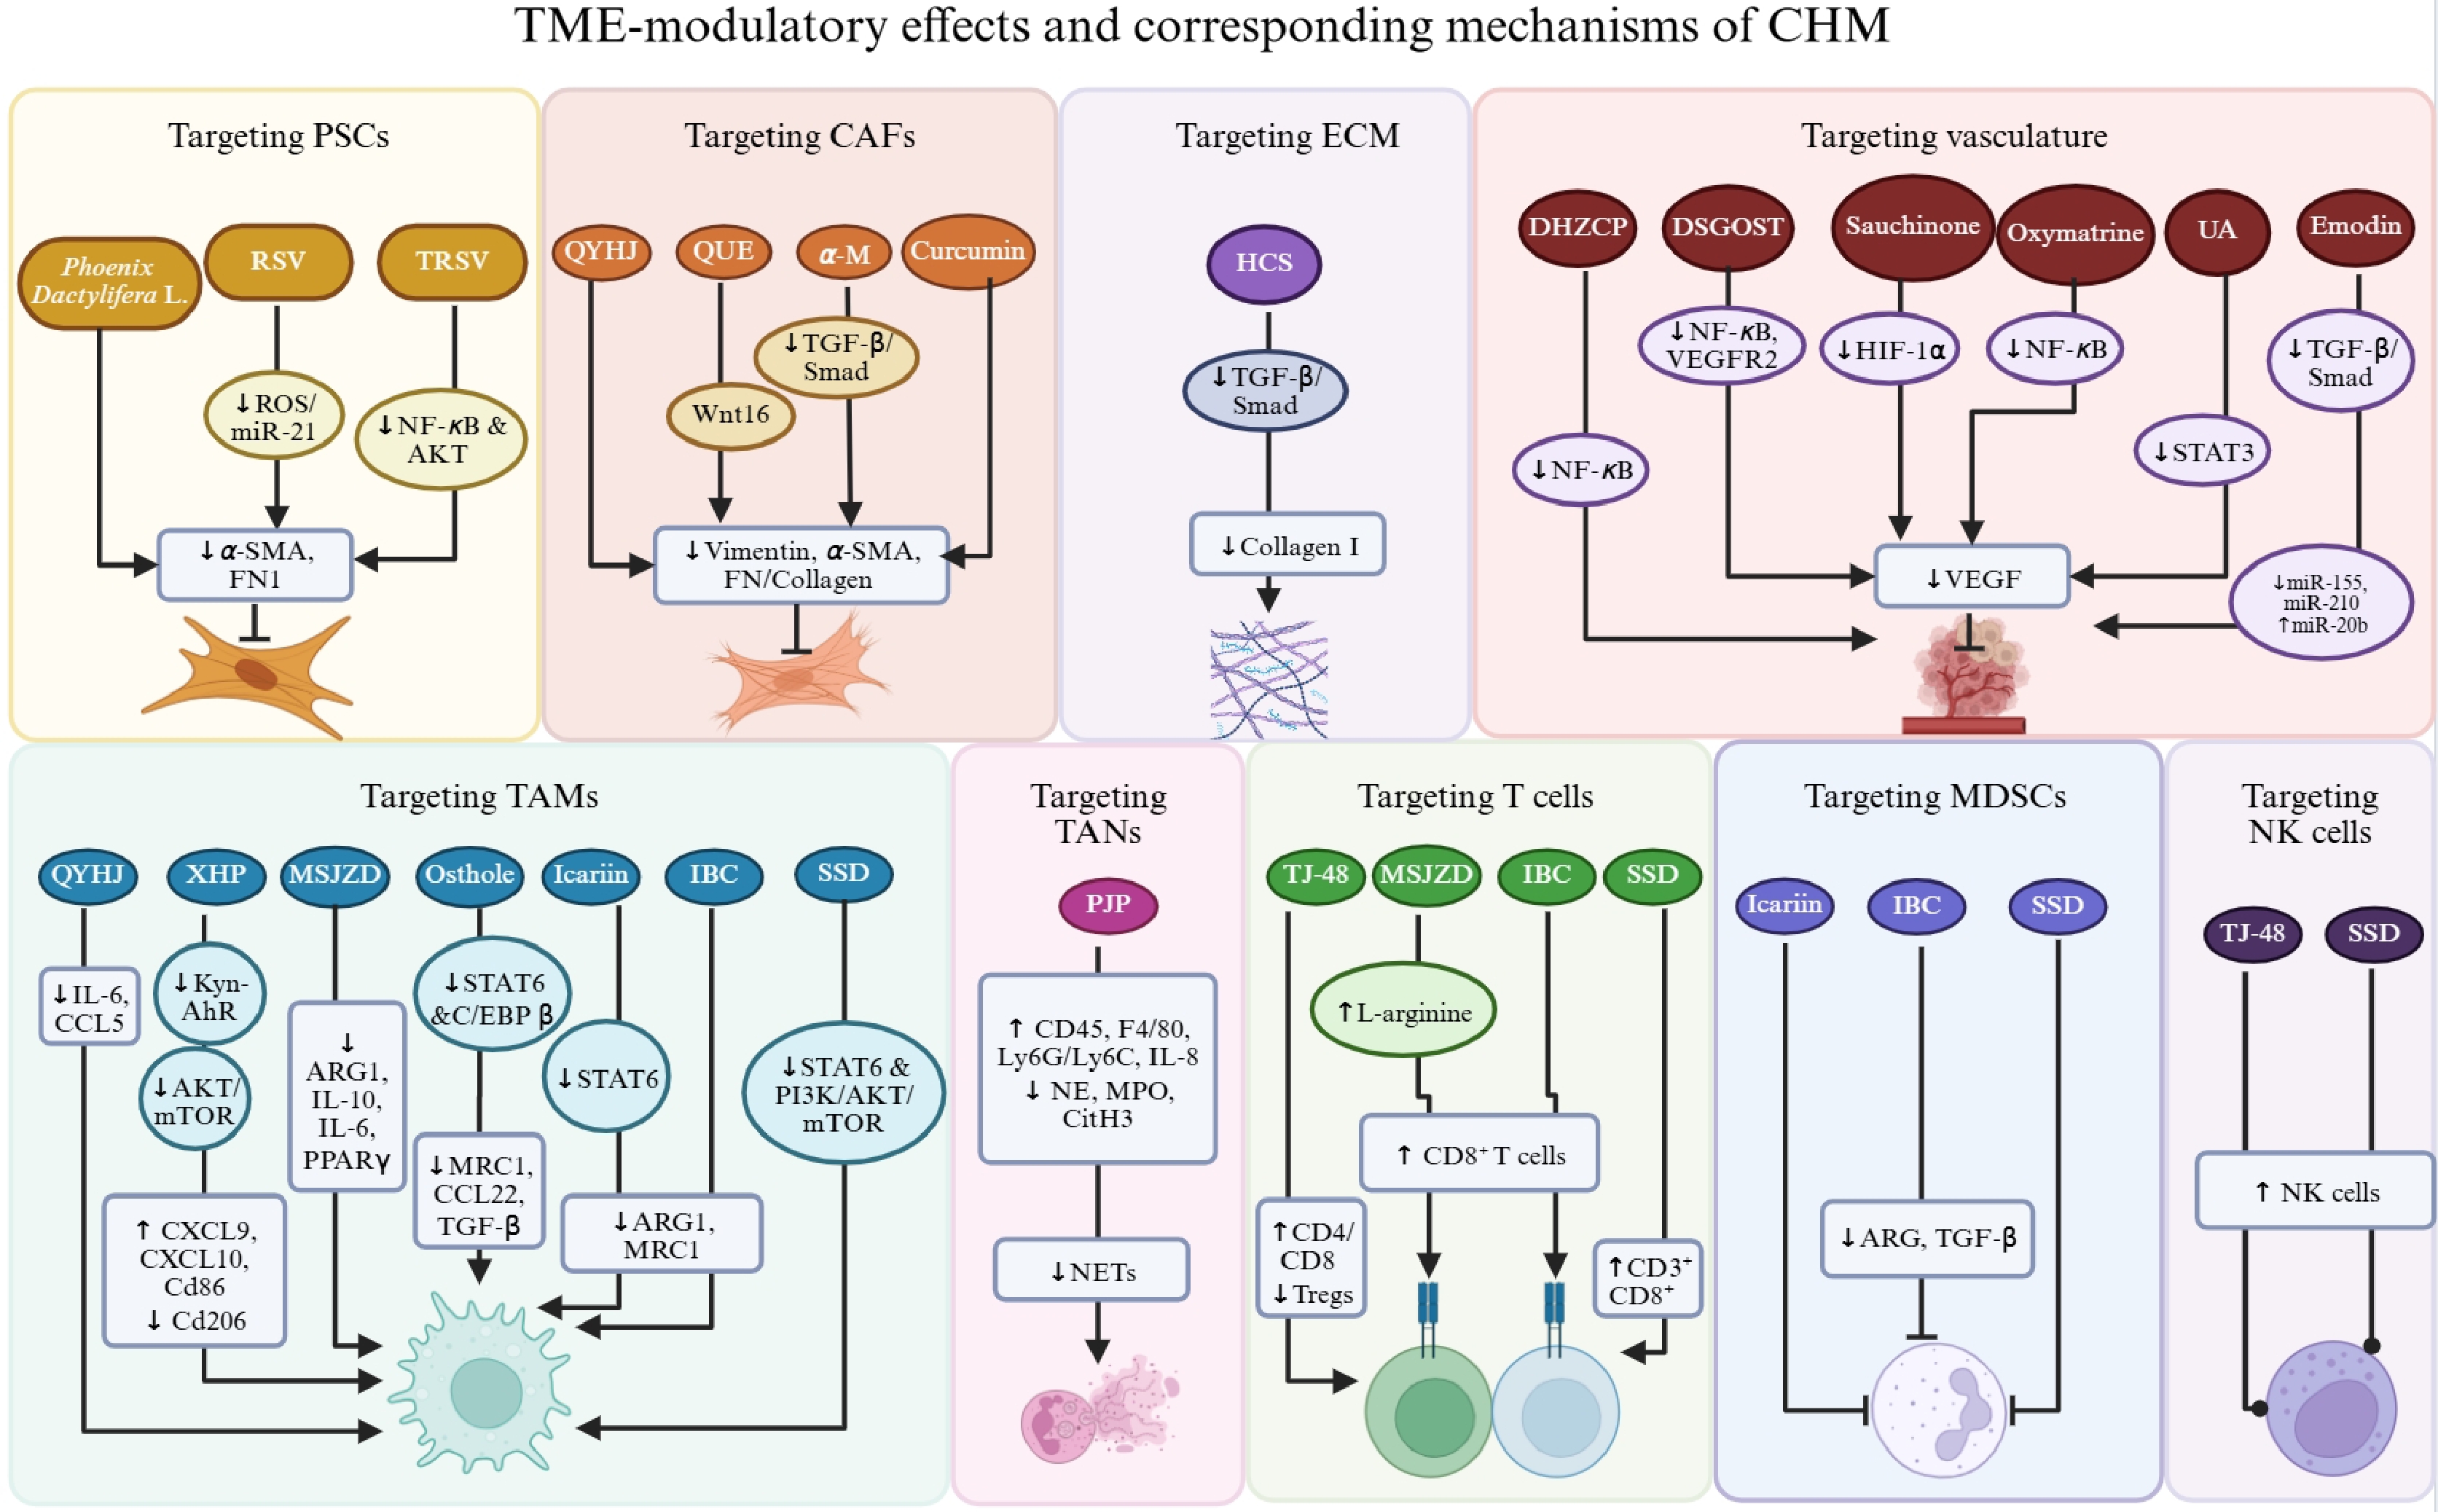
Figure 2.
Effects and mechanisms of CHM in targeting TME components. CHM inhibits the proliferation and activity of PSCs and CAFs, as well as remodeling of the ECM, via suppression of a variety of fibrotic mediators, miRNAs, and pathways such as TGF-β/Smad. Vasculature in the TME can be regulated by CHM mainly through inhibition of NF-κB-mediated VEGF, VEGF binding to VEGFR2, pathways including STAT3 and TGF-β/Smad, and modulation of miRNAs. Multiple tumor-infiltrating immune cells have been revealed as targets of CHM, including targeting the polarization of M1/M2 macrophages, inhibition of TAMs, MDSCs, TANs, and Treg infiltration, as well as increasing cytotoxic T cell and NK cell responses, involving cytokines and chemokines such as IL-6, ARG1, MRC1, TGF-β, and signaling pathways including STAT6 and PI3K/AKT/mTOR.
-
Although pre-clinical studies have demonstrated the therapeutic effectiveness of CHM in modulating the TME, clinical trials of CHM for treating PDAC by targeting the TME are still lacking. For instance, improvement in overall survival and quality of life after receiving CHM or integrative treatments remains the sole objective of clinical trials, while specific evaluation of their effects on the TME in real patients is neglected. For example, an ongoing trial investigating the efficacy of combined therapy of QYHJ and standard chemotherapy is designed to be measured primarily by overall survival and disease-free survival[100].
-
Toxicity, adverse effects, and potential drug–drug interactions remain major concerns and obstacles for the clinical application of CHM and its products. In order to gain comprehensive insight and provide evidence for the translational application of these CHMs, we summarize the known toxicity profiles of these selected CHMs by searching databases including TCMSP, TCM-ID, and Livertox, as shown in Table 2. The three formulae, QYHJ, DHZCP, and DSGOST, have one, five, and one herb recognized as toxic, respectively, while all single-herb extracts and active compounds are safe for use based on current findings.
Table 2. Toxicity of selected CHM.
CHM formulae/extract/
compoundsTarget Constituents/solvent/
originsToxicity Qingyihuaji formula CAFs, TAMs, vasculature Amorphopallus Ribieri Rhizoma Toxic Dahuang Zhechong pill Vasculature Toxicodendri Resina Slight Armeniacae Amarum Semen Toxic Holotrichia Sauteri Moser Extreme Hirudo Slight Persicae Semen Slight Danggui-Sayuk-Ga-Osuyu-Saenggang-Tang Vasculature Evodiae Fructus Slight Extreme: Causing severe adverse response at low dosage. Toxic: Therapeutic dose being close to toxic dose. Slight: Toxic when used in excess. -
As summarized above, CHM can modulate the TME in PDAC through multi-target and multi-pathway mechanisms. As for the stromal compartments, although in-depth mechanistic studies are still lacking, studies have shown that CHM can directly inhibit the activity and proliferation of PSCs, mainly by suppressing HIF-1α, α-SMA, and SDF-1 expression. α-SMA and vimentin are usually selected for the measurement of CAF activity, whose inhibition can be achieved by blocking the TGFβ/Smad signaling pathway. As for targeting vasculature, suppression of NF-κB-mediated VEGF and STAT3 signaling serves as the core mechanism of CHM effects in anti-angiogenesis, while modulation of miRNA is also involved. As for the immune compartments, most CHMs manifest inhibitory effects on M2-TAM infiltration and M2 polarization, with a decrease in M2-derived ARG1 and MRC1 expression, achieved by inhibition of the STAT6 and PI3K/AKT/mTOR signaling pathways. As M2 polarization participates in the promotion of MDSC recruitment and suppression of cytotoxicity of T cells and NK cells, restrained MDSC infiltration and increased CD8+ T cells and NK cells are also detected following the M2-TAM subpopulation, such as in MSJZD, IBC, and SSD treatment. Moreover, CHMs such as the QYHJ formula are able to target CAFs and TAMs, which belong to different compartments, at the same time. Therefore, CHMs possess the potential to systematically regulate the TME towards a baseline and even anti-tumor state through diverse signaling pathways and miRNA modulation.
There are a few limitations in the current literature regarding TCM in treating PDAC by targeting the TME. 1) The quality of current studies is yet to be improved. Among the limited literature, many are short of in-depth mechanistic investigation and validation; some are lacking in vivo models, while toxicity and safety evaluations of CHM are usually missing, which serve as obstacles to further promoting CHM in clinical trials and practice. 2) Clinical trials assessing both survival outcomes, quality of life, and TME-modulatory effects of CHM are extremely lacking, leading to the retardation of translational research progress. As for developing innovative medicines from CHM, challenges mainly result from difficulties in standardization and quality control of formulae and herbs, as well as low solubility, bioavailability, and stability of active compounds.
-
First, studies assessing modulatory effects of CHM on peripheral nerves and microbiota-mediated immunosuppression are still lacking. As mentioned above, neural compartments in the TME are able to recruit tumor-promoting immune cells and nourish PCCs, while microbiota-derived metabolites selectively induce tumor progression and immunosuppression[55−57,61,62]. CHM might be able to interrupt these actions by blocking infiltration of immune-suppressive cells, limiting release of signaling or nutrient molecules, and eliminating microbiota and its metabolites with its well-known anti-pathogenic effects. Second, several obstacles for clinical translation of CHM remain unsolved, including toxicity, safety profiles, and potential drug–herb interactions. Further investigation is required for the pharmacodynamic and pharmacokinetic understanding of these CHMs and their combination with modern medication. Additionally, standardization of CHMs is essential for consistency in experimental and clinical studies, with the advancement of chromatographic fingerprinting, standard-based quantification, and rigorous quality control and quality assurance. Last but not least, integration of TME-targeted CHMs and modern interventions exerts considerable potential that is worthy of further exploration, such as the prolonged survival of TJ-48 combined with the GFP (Gemcitabine, Fluorouracil [5-FU], and Platin [Cisplatin]) protocol in clinical trials[99], and well-designed, multi-center clinical trials are urgently needed for the validation of combinatorial strategies.
-
In conclusion, the heterogeneity and dynamics of the TME in PDAC bring not only stern challenges but also the possibility of modulating the surrounding environment of cancer cells towards a tumor-suppressive state. CHM has manifested multi-target and multi-pathway modulatory effects on TME components, indicating the therapeutic potential of integrating TCM and modern therapies against PDAC with the involvement of TME regulation.
-
Not applicable.
-
The authors confirm their contributions to this study as follows: conceived and designed the review, revised the manuscript: Lin ZX, Xian YF; retrieved the literature and drafted the manuscript: Xue LR; participated in the design of the study and assessed the quality of the study: Wu YL. All authors reviewed the results and approved the final version of the manuscript.
-
Data sharing not applicable to this article as no datasets were generated or analyzed during the current study.
-
The authors have no conflict of interest to declare.
- Copyright: © 2026 by the author(s). Published by Maximum Academic Press on behalf of China Pharmaceutical University. This article is an open access article distributed under Creative Commons Attribution License (CC BY 4.0), visit https://creativecommons.org/licenses/by/4.0/.
-
About this article
Cite this article
Xue LR, Wu YL, Lin ZX, Xian YF. 2026. Chinese Medicine for the treatment of pancreatic cancer by targeting the tumor microenvironment: mechanistic insights and therapeutic potential. Targetome 2(5): e050 doi: 10.48130/targetome-0026-0049 
Chinese Medicine for the treatment of pancreatic cancer by targeting the tumor microenvironment: mechanistic insights and therapeutic potential
- Received: 30 June 2026
- Revised: 25 August 2026
- Accepted: 01 September 2026
- Published online: 29 September 2026
Abstract: Pancreatic ductal adenocarcinoma (PDAC) is a highly lethal malignancy with aggressive progression and rapid development of therapeutic resistance. The tumor microenvironment (TME) has been gradually revealed as a major contributor to the interventional dilemma, which is composed of diverse cellular and acellular components, constructing a desmoplastic and immunosuppressive pro-tumorigenic environment for cancer cells. The heterogeneity, plasticity, and dynamic interplay of these components give rise to complex compensatory responses to therapies, requiring a comprehensive, multi-target remodeling strategy. Chinese herbal medicine (CHM) has been suggested to exert effects in modulating the TME and thus suppressing tumor growth and enhancing the efficacy of conventional therapies. Based on insights into the complex TME and its role in metastasis and resistance, this review summarizes findings from studies that explore the modulatory effects of CHM classified by the components it targets, revealing the therapeutic potential of CHM and prospects for innovative intervention strategies and approaches.